
PCSK9 options widen as statins anchor cholesterol care
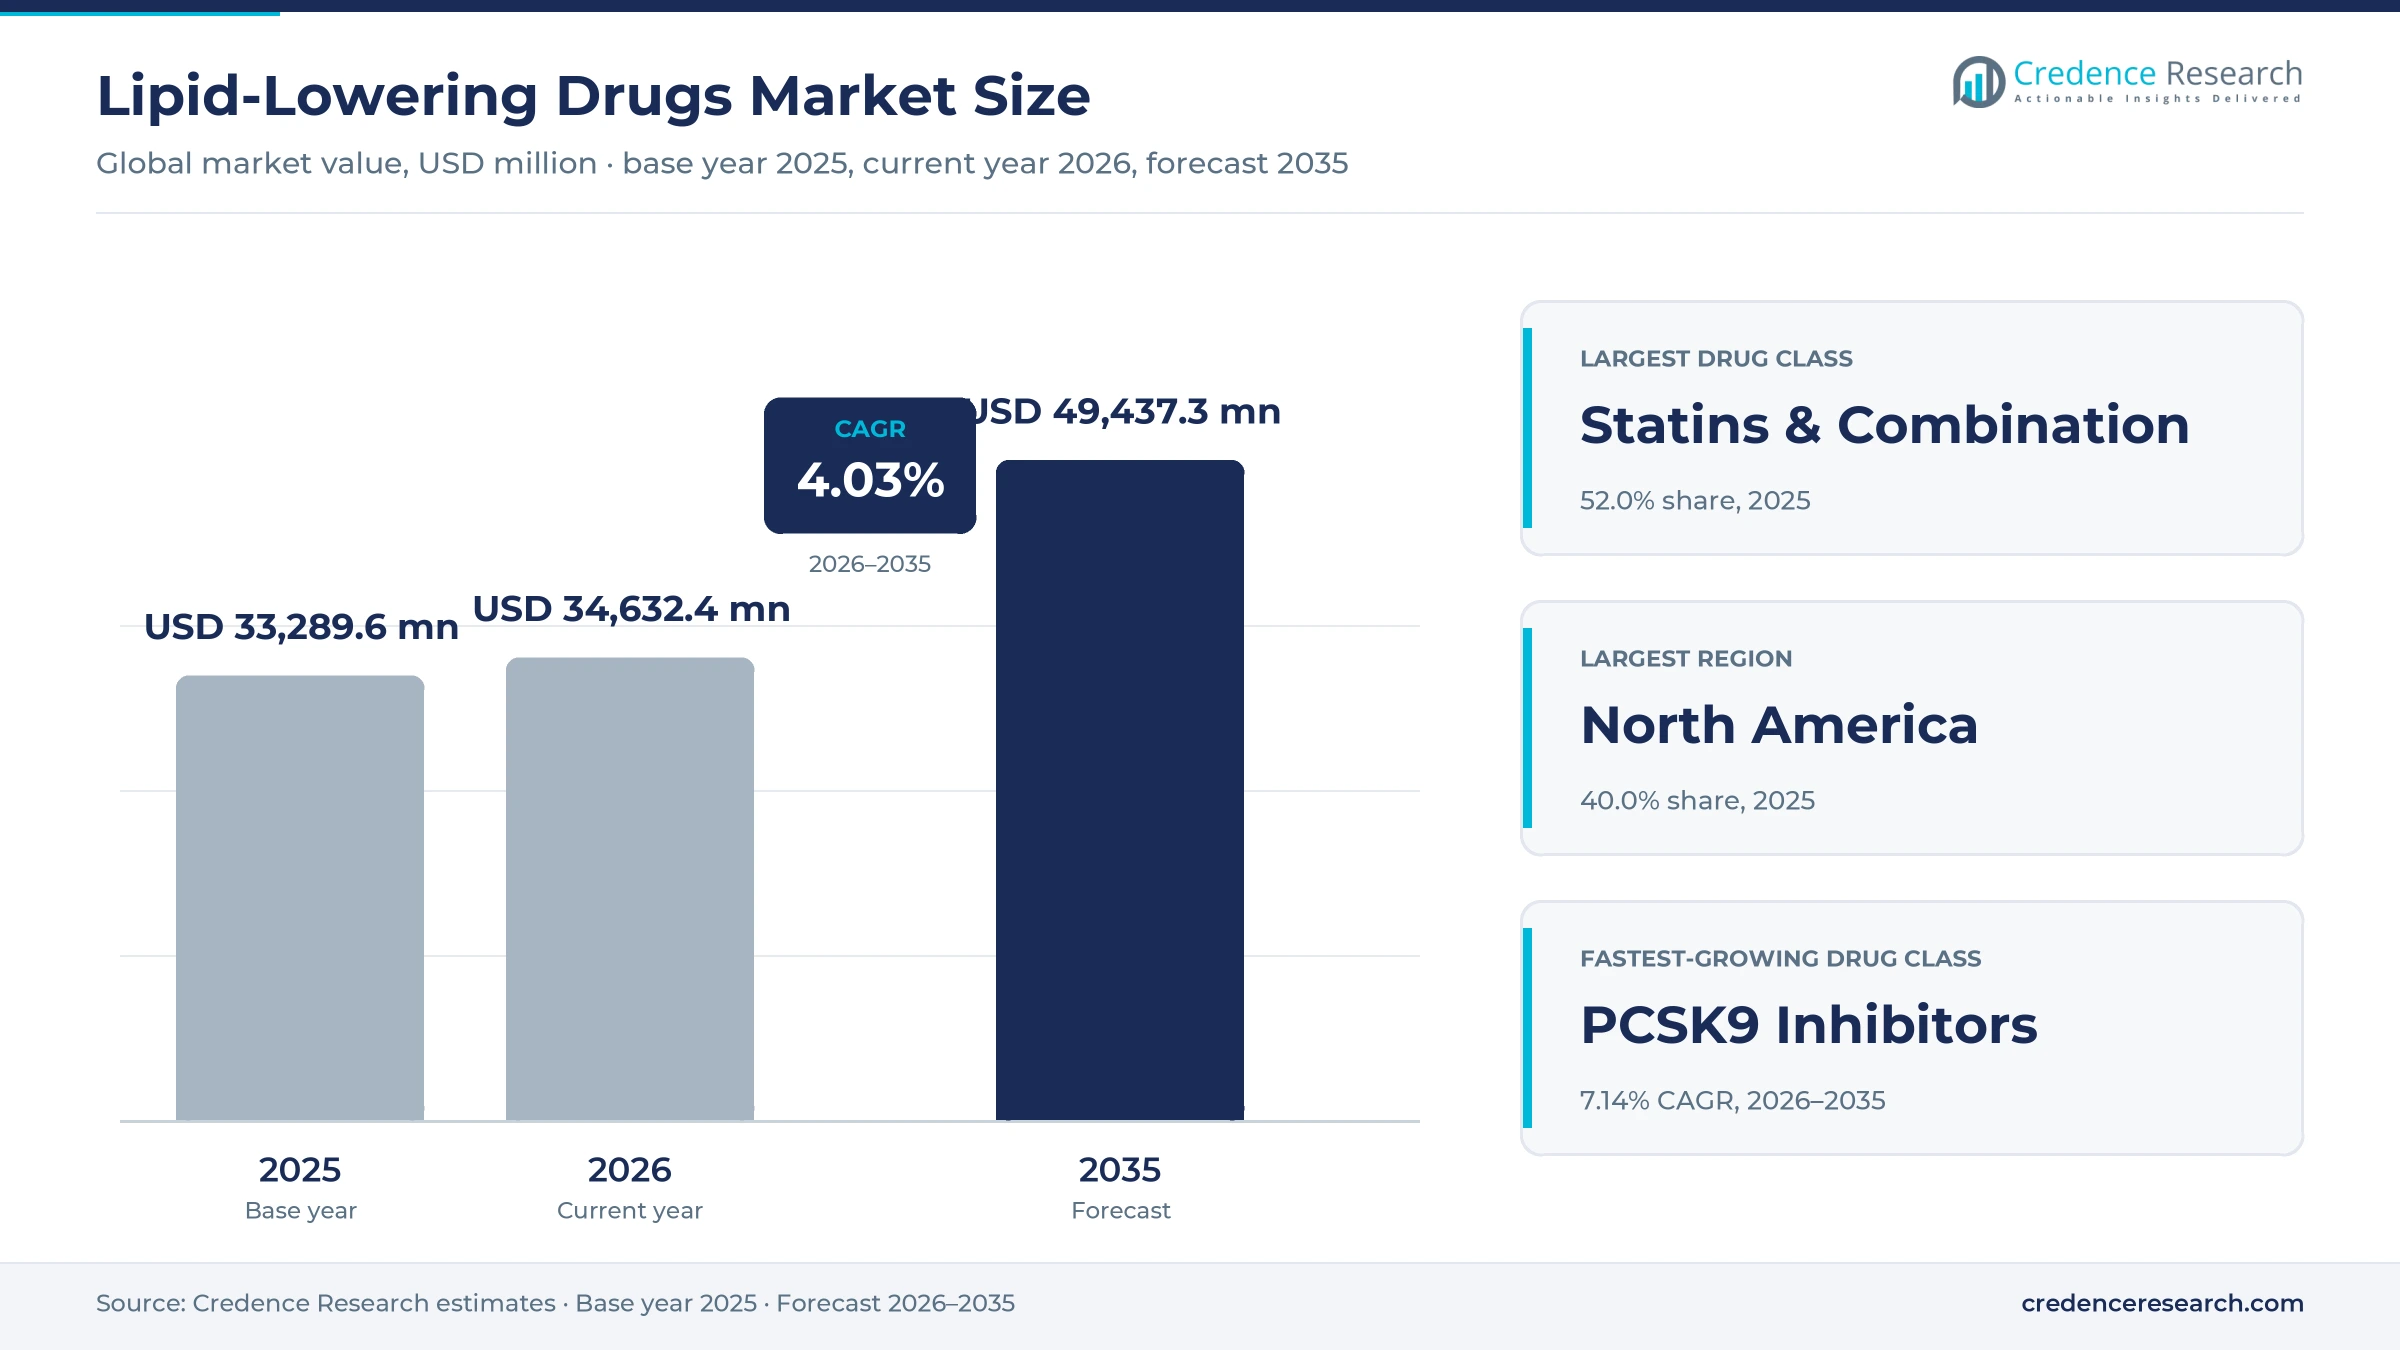
The global lipid-lowering drugs market was valued at USD 33.29 billion in 2025 and is projected to increase from USD 34.63 billion in 2026 to USD 49.44 billion by 2035, registering a CAGR of 4.03% during 2026–2035. Demand comes from the large number of adults with high LDL cholesterol, wider use of combination therapy after heart attacks and strokes, and new medicines that lower cholesterol with fewer doses. North America held the largest regional share, 40.0% in 2025, because branded PCSK9 therapies carry high prices and broad insurance coverage. Asia Pacific is the fastest-growing region at 5.19% a year, as China and India screen more adults and expand access to statins and newer agents. The treatment picture changed in July 2026, when the FDA approved the first once-daily oral PCSK9 inhibitor for adults with hypercholesterolemia. As a result, potent LDL lowering no longer depends only on injections.
Which cholesterol medicines and channels does this analysis cover?
The analysis counts prescription medicines that lower LDL cholesterol or triglycerides, including statins and statin combinations, PCSK9 inhibitors, cholesterol absorption inhibitors, fibrates, bile acid sequestrants and newer classes, valued at manufacturer selling prices. Patients fill most prescriptions through retail pharmacies, while hospitals start therapy after cardiac events.
Dietary supplements sold without a prescription, diagnostic tests and lipid apheresis procedures sit outside the scope of this analysis. The value chain runs from active ingredient suppliers through originator and generic manufacturers to wholesalers, pharmacies and payers, which set formulary access, prior authorization rules and patient costs.
Lipid-Lowering Drugs Market Insights
- The lipid-lowering drugs market grows from USD 33.29 billion in 2025 to USD 49.44 billion by 2035, a 4.03% CAGR as potent LDL therapy reaches more patients.
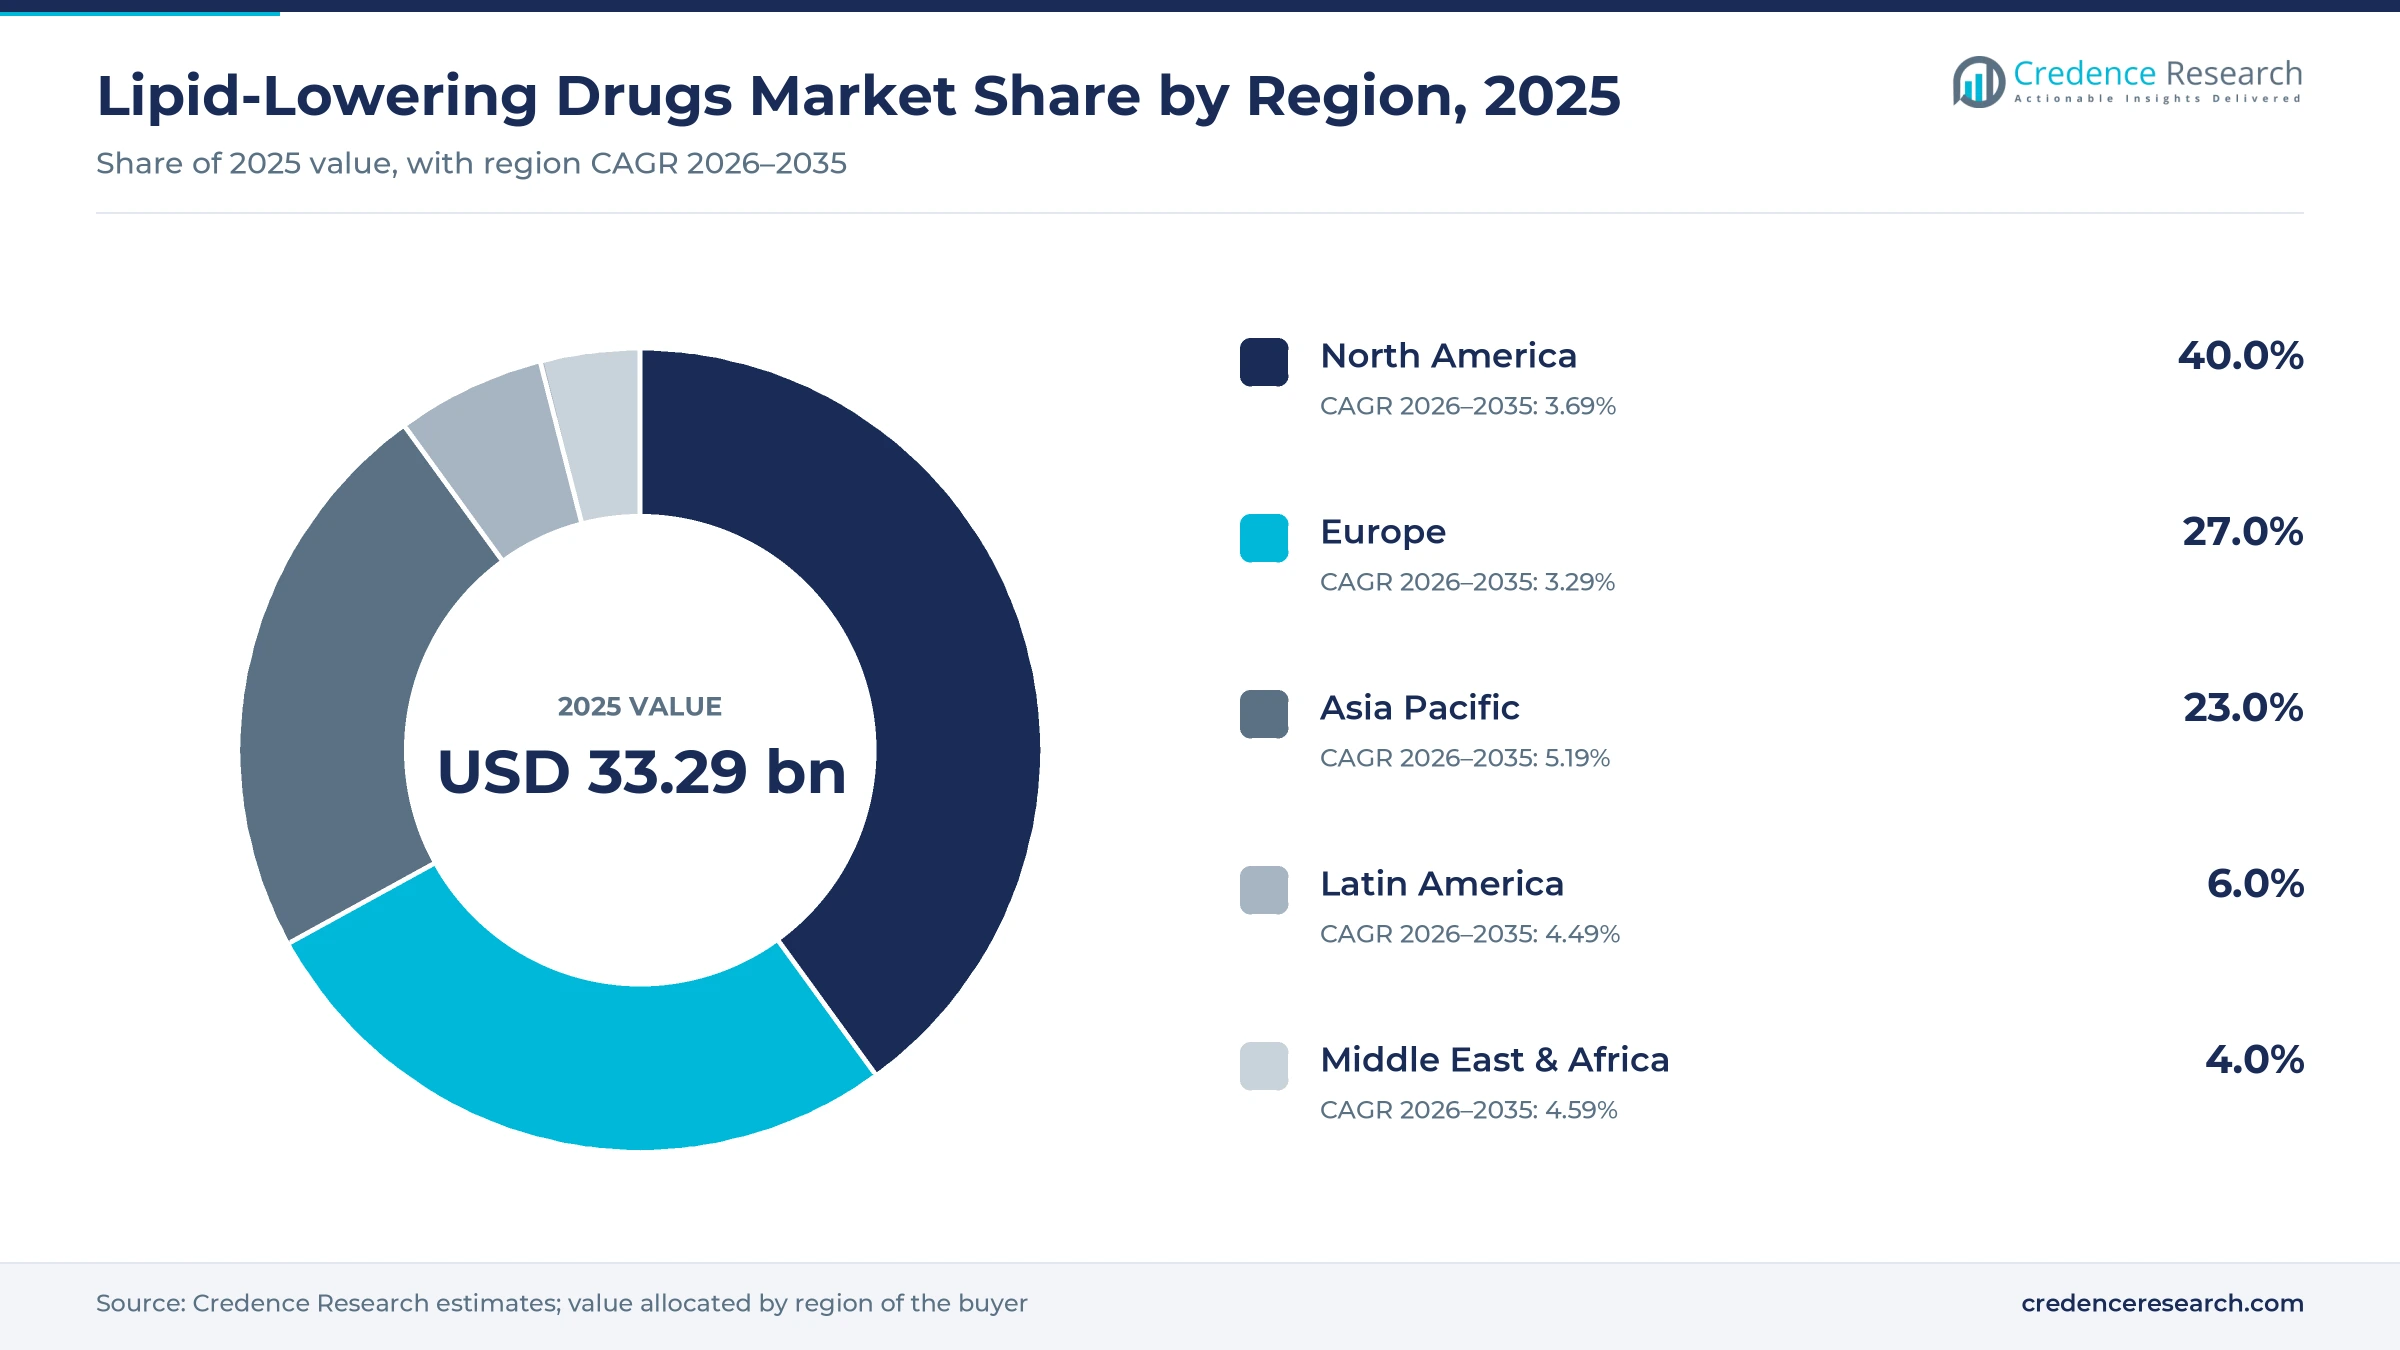
- North America held 40.0% of global cholesterol medicine value in 2025, supported by high prices for branded PCSK9 therapies.
- Statins and statin combinations led drug classes with 52.0% of 2025 value, because they remain first-line therapy worldwide.
- In July 2026, the FDA approved Merck Lipfendra, the first once-daily oral PCSK9 inhibitor, for adults with hypercholesterolemia.
- In November 2025, Amgen reported that Repatha cut the risk of a first major cardiovascular event by 25% in the VESALIUS-CV trial.
Statins lead as PCSK9 inhibitors gain fastest
Why do statins still lead cholesterol spending?
Based on drug, the market is categorized into statins and combination, PCSK9 inhibitors, bile acid sequestrants, fibrates, cholesterol absorption inhibitors and others. Statins & Combination led with a 52.0% share of 2025 value, because guidelines recommend statins as first-line therapy for most patients. PCSK9 Inhibitors grow fastest at 7.14% a year, as twice-yearly injections and a new oral pill add options for patients who miss LDL targets on statins alone.
How does hypercholesterolemia shape demand by indication?
Based on indication, the market is categorized into hypercholesterolemia, coronary artery disease and high triglycerides. Hypercholesterolemia led with 62.0% of 2025 value, because most prescriptions treat elevated LDL cholesterol before or after cardiac events. High Triglycerides grows fastest at 4.93% a year, as new RNA medicines target severe triglyceride disorders such as familial chylomicronemia syndrome.
Where do patients fill cholesterol prescriptions?
Based on distribution channel, the market is categorized into retail pharmacy, hospital pharmacy and online pharmacy. Retail Pharmacy led with a 64.0% share of 2025 value, because patients refill daily tablets near home. Online Pharmacy grows fastest at 6.01% a year, as online pharmacy platforms offer home delivery and automatic refills for chronic patients who take statins or ezetimibe every day for many years.
| Segment Group | Leading Sub-segment | Share, 2025 | Fastest-growing Sub-segment | CAGR, 2026–2035 |
|---|---|---|---|---|
| By Drug | Statins & Combination | 52.0% | PCSK9 Inhibitors | 7.14% |
| By Indication | Hypercholesterolemia | 62.0% | High Triglycerides | 4.93% |
| By Distribution Channel | Retail Pharmacy | 64.0% | Online Pharmacy | 6.01% |
Request a Free Sample
Fill in your details and we'll send you a free sample report.
- Sample data tables & charts
- Research methodology
Unmet LDL targets and outcome data lift treatment demand
How does the large high-cholesterol population sustain demand?
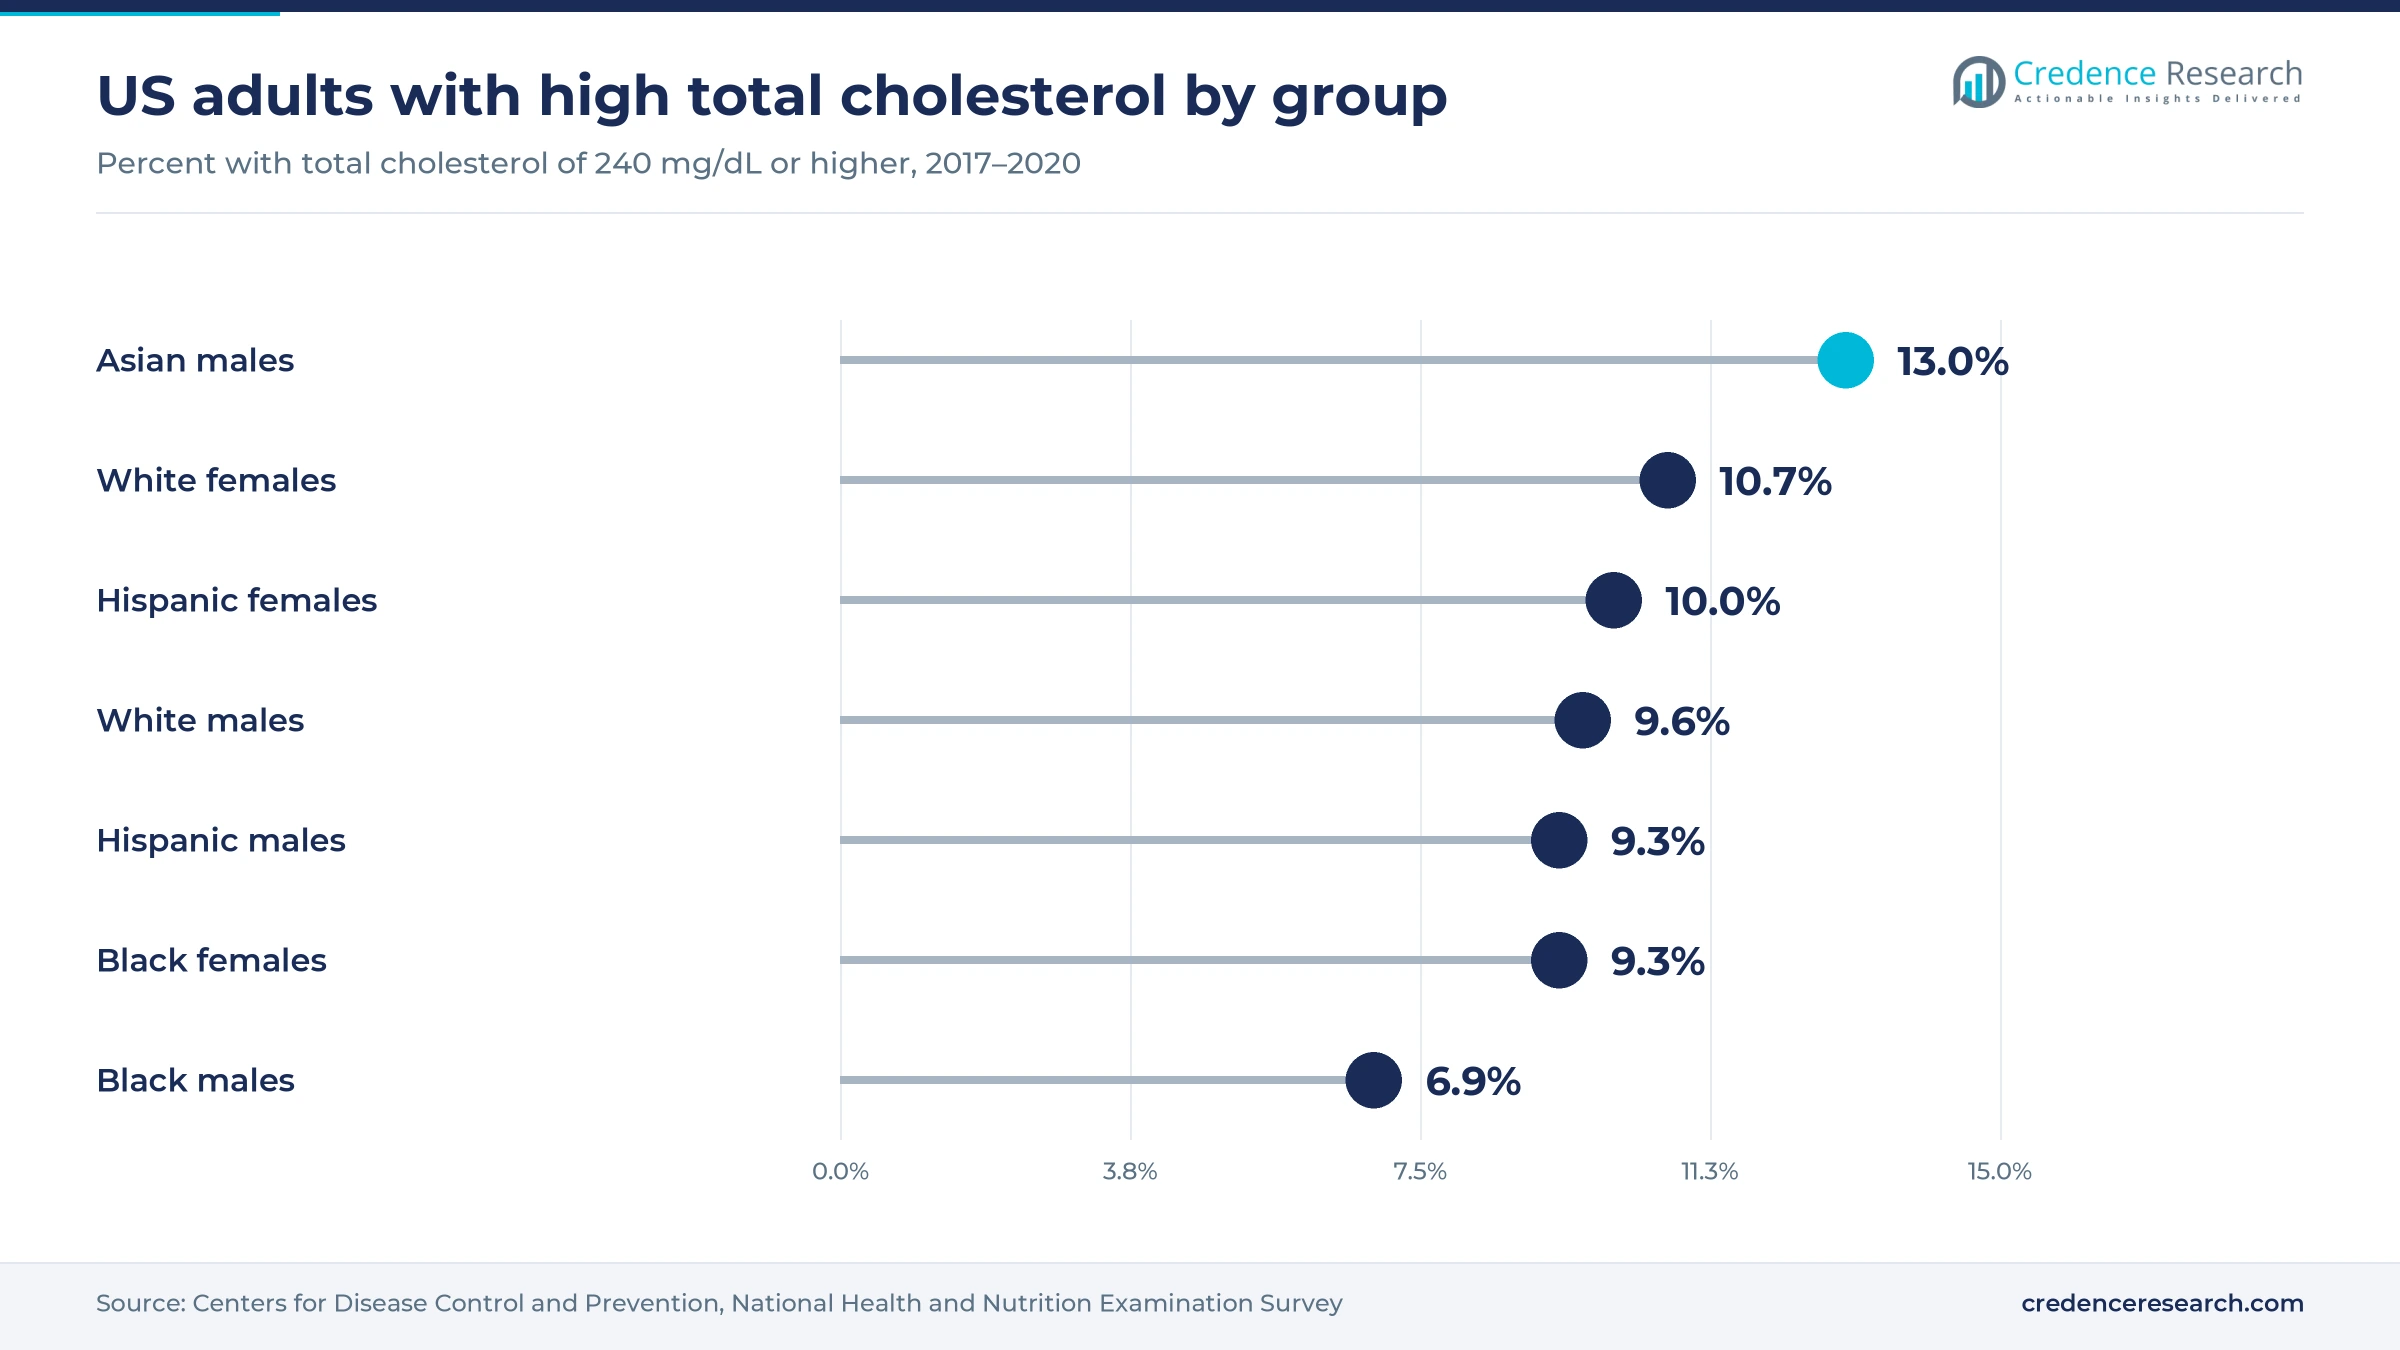
The large high-cholesterol population sustains demand, because most patients need lifelong therapy once treatment starts. The Centers for Disease Control and Prevention reports that about 10% of U.S. adults aged 20 and older had total cholesterol of 240 mg/dL or higher during 2017 to 2020. About 17% of U.S. adults also had low HDL cholesterol below 40 mg/dL in the same period. As a result, screening programs in the United States and abroad keep adding patients who need statins or combination therapy.
Why do unmet LDL targets push combination therapy?
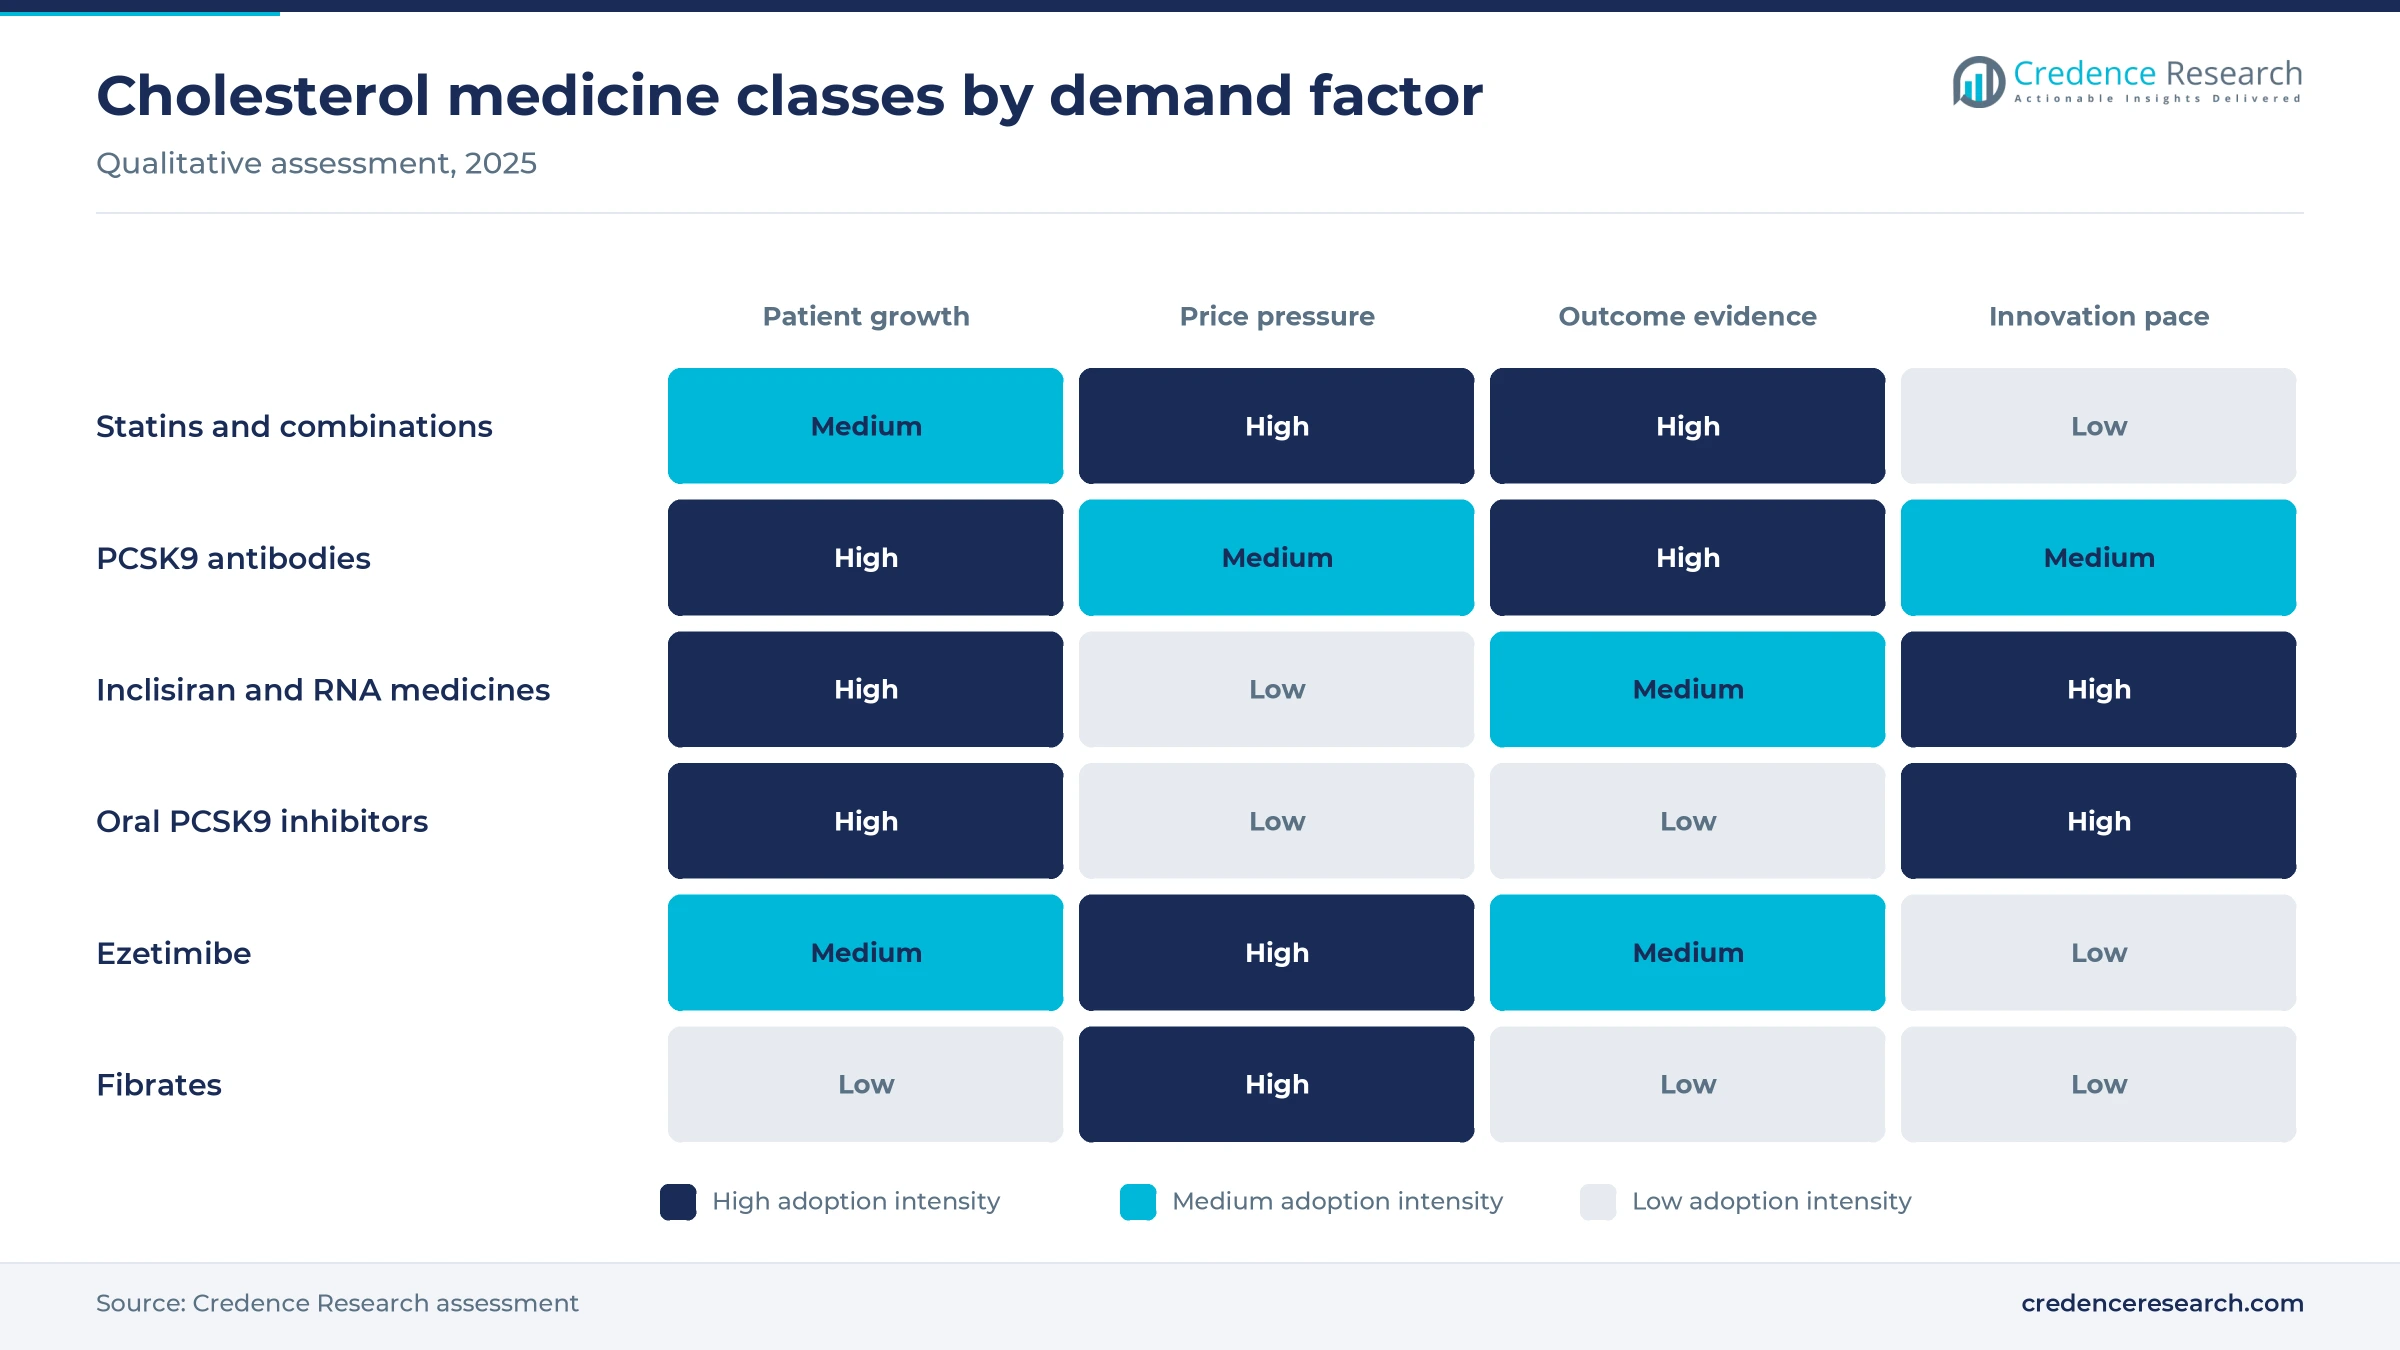
Unmet LDL targets push combination therapy, because many high-risk patients stay above guideline goals on statins alone. Novartis reports that about four in five patients with atherosclerotic cardiovascular disease do not reach the guideline LDL target, and this disease accounts for 85% of cardiovascular deaths. Up to 80% of these patients in the United States struggle to reach an LDL level below 70 mg/dL. In turn, clinicians add ezetimibe, PCSK9 therapies or other agents, which raises spending per treated patient through 2035.
How do outcome trials widen the eligible population?
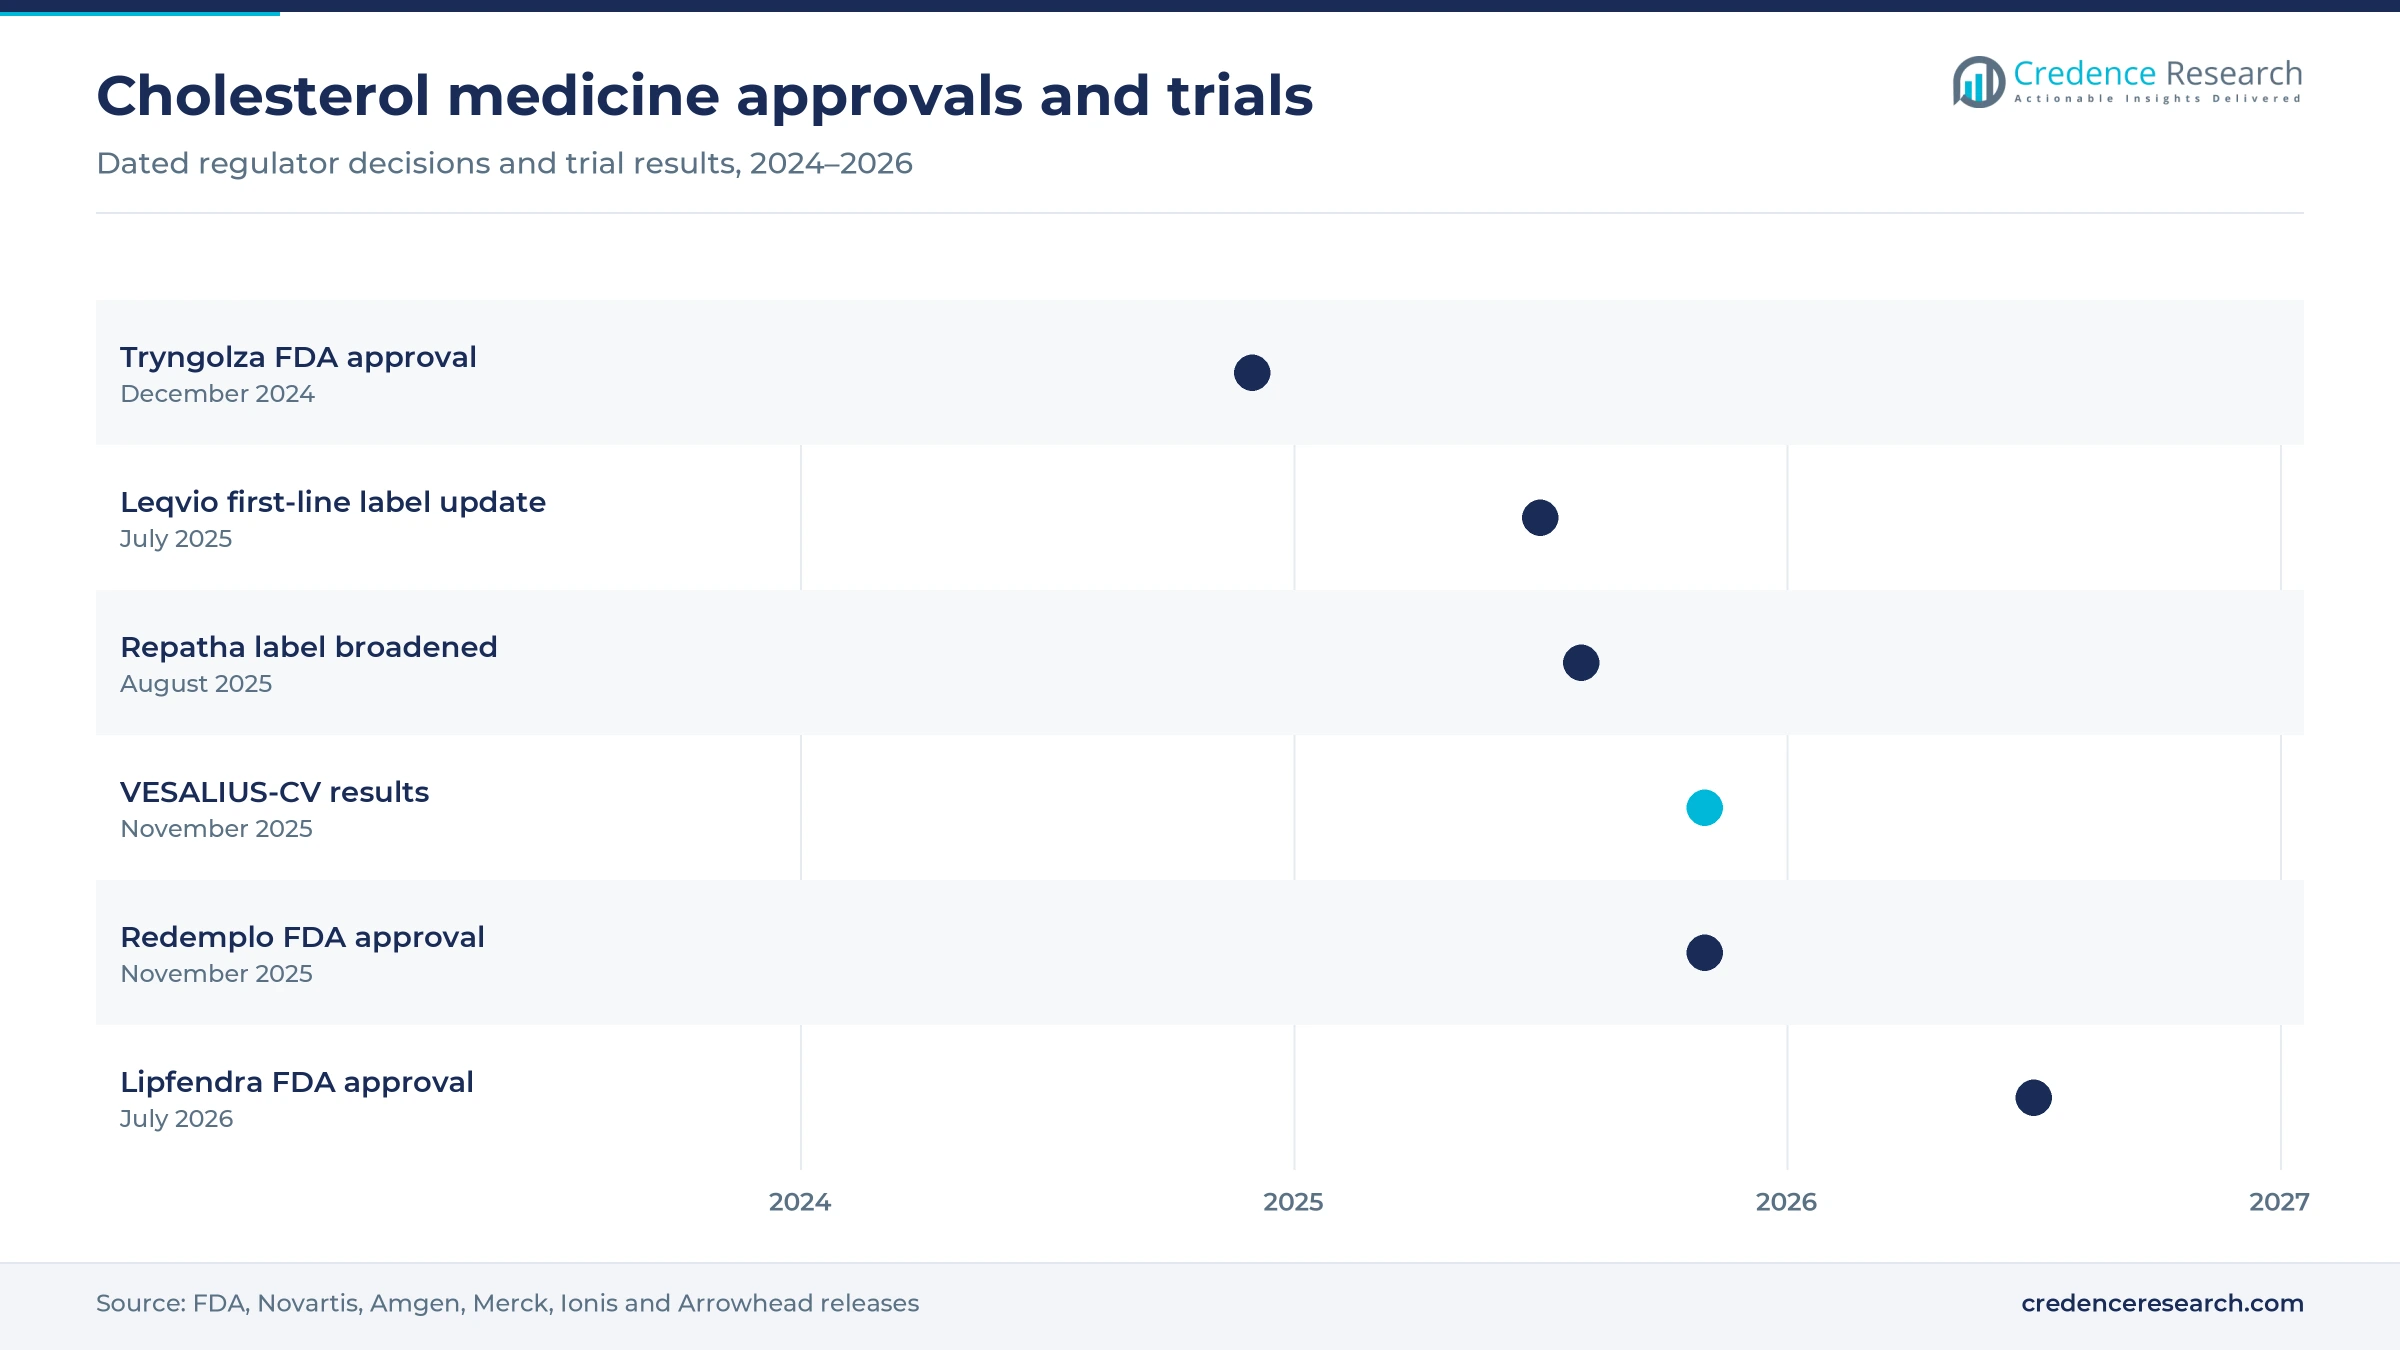
Outcome trials widen the eligible population, because payers and guideline groups respond to evidence of fewer heart attacks and strokes. In November 2025, Amgen reported VESALIUS-CV results showing that Repatha cut the risk of a first major cardiovascular event by 25% in more than 12,000 high-risk adults. Heart attack risk fell by 36% in the same trial. As a result, PCSK9 therapy can move earlier into prevention for patients without a prior cardiac event.
Why do label expansions support earlier use of potent therapy?
Label expansions support earlier use of potent therapy, because they remove restrictions that once limited treatment to patients with established disease. In August 2025, Amgen announced that the FDA broadened Repatha use to adults at increased risk of major adverse cardiovascular events due to uncontrolled LDL cholesterol. In July 2025, Novartis announced FDA approval of a Leqvio label update that allows use without a statin as first-line therapy. In turn, more patients with high LDL cholesterol qualify for PCSK9-targeted treatment in primary care.
Oral PCSK9 pills and twice-yearly doses reshape care
How is the shift to oral PCSK9 pills reshaping care?
The shift to oral PCSK9 pills is reshaping care, because many patients and clinicians prefer tablets to self-injection. In July 2026, Merck announced FDA approval of Lipfendra, a once-daily oral PCSK9 inhibitor, for adults with hypercholesterolemia, including heterozygous familial hypercholesterolemia. Trials showed placebo-adjusted LDL reductions of 56% and 59% at week 24 with one 20 mg tablet a day. As a result, primary care doctors can start potent therapy without injection training.
Why are twice-yearly injections rising in prevention?
Twice-yearly injections are rising in prevention, because poor adherence to daily pills limits the benefit of statins over time. Leqvio is given by a healthcare provider twice a year after an initial dose and a second dose at three months. This schedule fits routine clinic visits and removes the need for daily dosing, which suits older patients who take many other medicines. In turn, health systems can track adherence directly, which supports value-based contracts with payers.
Can triglyceride-targeting RNA medicines open new value?
Triglyceride-targeting RNA medicines give makers a clear opening, because severe triglyceride disorders had few effective treatments. In December 2024, the FDA approved Ionis Tryngolza for familial chylomicronemia syndrome, given once every four weeks by injection, after trials showed a 57% placebo-adjusted triglyceride reduction at 12 months. In November 2025, the FDA approved Arrowhead Redemplo, which reduced triglycerides by about 80% at the 25 mg dose in its trial. As a result, the high triglycerides segment adds premium products through 2035.
Where can better testing add treated patients?
Better testing gives manufacturers room to add treated patients, because many adults with high cholesterol remain undiagnosed. Low-cost cholesterol testing kits and pharmacy screening programs help identify these patients outside clinics. Patients with confirmed results can then start therapy through primary care or pharmacists, which shortens the path to treatment. Healthy adults are advised to check cholesterol every four to six years. In turn, companies that support screening can grow volume for both generic statins and newer branded agents.
Generic statins, payer limits and adherence slow value
Why does generic statin pricing limit value growth?
Generic statin pricing limits value growth, because most statins and ezetimibe are sold as low-cost generics worldwide. Generic makers such as Sun Pharmaceutical Industries, Viatris and Dr Reddys Laboratories compete on price and volume rather than on new data. This keeps spending per patient low for the largest drug class. As a result, value growth depends heavily on newer branded agents rather than on volume.
How do payer restrictions slow uptake of branded therapy?
Payer restrictions slow uptake of branded therapy, because insurers often require prior authorization and proof of statin failure first. These steps add paperwork for clinicians and delay treatment for high-risk patients, including those with familial hypercholesterolemia. Many patients abandon prescriptions when approval takes weeks or copays stay high. In turn, use of PCSK9 therapies remains below the levels suggested by the number of patients who miss LDL targets, even after the 2025 label expansions.
Why does poor adherence reduce treatment benefit?
Poor adherence reduces treatment benefit, because high cholesterol causes no symptoms and patients often stop daily pills. Concerns about muscle pain and other side effects lead some patients to quit statins within the first year. This problem raises the risk of heart attacks and strokes over time. In turn, clinicians need follow-up visits and lipid testing, which many primary care practices cannot provide for every patient.
How do access gaps slow treatment in low-income countries?
Access gaps slow treatment in low-income countries, because lipid testing and long-term prescriptions are not widely available. Many patients receive no therapy until after a heart attack or stroke, when the benefit of prevention is reduced. Branded PCSK9 medicines are priced out of reach for most public programs in these markets. As a result, generic statins remain the main option for most patients through the forecast period.
North America leads as Asia Pacific gains pace
| Region | Value, 2025 (USD billion) | Share, 2025 | CAGR, 2026–2035 |
|---|---|---|---|
| North America | 13.32 | 40.0% | 3.69% |
| Europe | 8.99 | 27.0% | 3.29% |
| Asia Pacific | 7.66 | 23.0% | 5.19% |
| Latin America | 2.00 | 6.0% | 4.49% |
| Middle East & Africa | 1.33 | 4.0% | 4.59% |
Why does North America hold the largest regional share?
North America held a 40.0% share of 2025 value and grows at 3.69% a year through 2035. The United States drives this position, because branded PCSK9 therapies and combination products carry high list prices. New medicines such as Lipfendra and Redemplo launched first in this market after FDA approval. However, generic statins and payer restrictions keep average spending per patient in check.
How fast is Asia Pacific adding treated patients?
Asia Pacific held a 23.0% share of 2025 value and is the fastest-growing region at 5.19% a year. China, India and Japan carry large populations with high cholesterol and rising coronary artery disease. Wider screening and public coverage add new patients each year, while local generic makers such as Sun Pharmaceutical Industries supply affordable statins. As a result, the region adds the largest number of new patients through 2035.
What shapes demand across Europe?
Europe held a 27.0% share of 2025 value and grows at 3.29% a year, the slowest pace of the five regions. Germany, the United Kingdom, France, Italy and Spain account for most spending through national formularies. Health systems use hospital tenders and reference pricing to manage spending on newer branded agents. However, strict price controls keep value growth below the global average.
Where is Latin America adding demand?
Latin America held a 6.0% share of 2025 value and grows at 4.49% a year through 2035. Brazil and Mexico lead regional spending, while public programs supply generic statins to many patients.
What limits growth in the Middle East and Africa?
The Middle East and Africa held a 4.0% share of 2025 value and grows at 4.59% a year through 2035. Gulf states fund branded therapies, while much of Africa relies on low-cost statins and limited lipid testing.
Approvals and outcome trials in cholesterol care since 2024
| Development | Status and market relevance |
|---|---|
| In December 2024, the FDA approved Ionis Tryngolza for adults with familial chylomicronemia syndrome. | Approved; once-every-four-weeks injection that lowers triglycerides |
| In July 2025, the FDA approved a Leqvio label update that allows first-line use without a statin. | Approved; twice-yearly inclisiran for adults with hypercholesterolemia |
| In August 2025, Amgen announced that the FDA broadened Repatha use to adults at increased cardiovascular risk. | Approved; removes the need for a prior cardiovascular disease diagnosis |
| In November 2025, Amgen reported VESALIUS-CV results showing a 25% cut in first major cardiovascular events with Repatha. | Completed; supports earlier PCSK9 use in prevention |
| In July 2026, the FDA approved Merck Lipfendra, the first once-daily oral PCSK9 inhibitor. | Approved; for adults with hypercholesterolemia including heterozygous familial forms |
RNA medicines and oral peptides lead innovation
- Small interfering RNA therapy silences genes such as PCSK9 in the liver, which allows dosing only twice a year.
- Oral macrocyclic peptides block PCSK9 in tablet form, which brings potent LDL lowering to patients who avoid injections.
- Antisense oligonucleotides reduce apolipoprotein C-III, which lowers triglycerides in rare and severe lipid disorders.
- Fixed-dose combination tablets pair a statin with ezetimibe, which simplifies daily dosing and supports adherence.
- Monoclonal antibody pens deliver PCSK9 antibodies every two to four weeks, which gives patients a home option.
Need a Custom Version of This Report?
Tailor the scope, geography, or segments to your exact requirements.
- Custom geography or segment scope
- Direct access to our analyst team
Originators and generic makers compete on price and data
Competition is led by originators with PCSK9 and RNA programs and by generic makers with large statin portfolios. Amgen Inc., Novartis AG and Merck lead branded LDL lowering through Repatha, Leqvio and Lipfendra, and each gained an FDA approval or label change since 2025. Sanofi, AstraZeneca PLC and Pfizer participate through cardiovascular portfolios, partnerships and earlier lipid products. GlaxoSmithKline plc, Takeda Pharmaceutical Company Limited and AbbVie hold smaller positions in older or regional cholesterol products. Viatris, Sun Pharmaceutical Industries Ltd. and other generic makers compete on statin and ezetimibe volume, where manufacturing scale matters most. As a result, competition increasingly centers on outcome data, dosing convenience and payer access for high-risk patients across cardiovascular medicines as a whole.
Companies profiled and their roles in this market
| Company | Type | Role in the market |
|---|---|---|
| Amgen Inc. | Originator | Repatha PCSK9 antibody with VESALIUS-CV outcome data |
| Novartis AG | Originator | Twice-yearly Leqvio inclisiran |
| Merck & Co., Inc. | Originator | Lipfendra oral PCSK9 inhibitor |
| Sanofi | Originator | Cardiovascular and lipid portfolio |
| AstraZeneca PLC | Originator | Statin brands and cardiovascular pipeline |
| Pfizer, Inc. | Originator | Established statin brands |
| GlaxoSmithKline plc | Originator | Older lipid products in selected markets |
| Takeda Pharmaceutical Company Limited | Originator | Cardiovascular products in Japan and Asia |
| AbbVie, Inc. | Originator | Fibrate and lipid products |
| Viatris (Mylan N.V.) | Generic and branded | Generic statins and established brands |
| Sun Pharmaceutical Industries Ltd. | Generic | Generic statins and combinations in emerging markets |
| Dr. Reddy's Laboratories Ltd. | Generic | Generic lipid medicines in the U.S. and emerging markets |
Earlier use of potent therapy sets the pace to 2035
Credence Research's view is that earlier use of potent therapy will set the pace of change through 2035, while generic statins keep volumes high and prices low. The overall market grows at 4.03% a year, supported by PCSK9 outcome data, twice-yearly dosing and the first oral PCSK9 pill. Payer restrictions and poor adherence restrain uptake of branded agents in many markets. Companies that pair convenient dosing with strong outcome evidence and payer access will win the most patients.
How Credence Research sized cholesterol medicine spending
The report uses 2025 as the base year and 2026 to 2035 as the forecast period. Market values come from the Credence Research model, which builds spending by drug, indication, distribution channel and region. Regional and segment splits are Credence Research estimates informed by Centers for Disease Control and Prevention statistics, FDA decisions and company press releases. No primary interviews or surveys were used in preparing this edition of the report.
Cholesterol medicine spending outlook to 2035
By 2035, the lipid-lowering drugs market is projected to reach USD 49.44 billion, with growth led by PCSK9 therapies, RNA medicines and wider treatment in Asia Pacific. Statins and combinations will remain the largest drug class, while oral and twice-yearly PCSK9 options gain share. North America keeps the highest spending per patient, although generic statins and payer limits restrain price growth. Online pharmacies will handle a larger share of chronic refills over the decade. As a result, advantage will depend on outcome data, convenience and access.
Frequently Asked Questions
How big is the global lipid-lowering drugs market?
Which drug class leads the lipid-lowering drugs market?
Which region leads cholesterol medicine spending?
Which indication grows fastest?
How common is high cholesterol in the United States?
What is the first oral PCSK9 inhibitor?
Who are the leading lipid-lowering drug companies?
What restrains growth in lipid-lowering drugs?
Table of Content
Chapter 1 Market Segmentation
- 1.1 Segmentation Framework
- 1.1.1 Product and Service Classification
- 1.1.2 Application and End-Use Classification
- 1.1.3 Technology and Solution Classification
- 1.1.4 Customer and Distribution Channel Classification
- 1.1.5 Geographic Segmentation
- 1.1.6 Market Segment Definitions and Boundaries
- 1.2 By Drug
- 1.2.1 Statins & Combination
- 1.2.2 PCSK9 Inhibitors
- 1.2.3 Cholesterol Absorption Inhibitors
- 1.2.4 Fibrates
- 1.2.5 Bile Acid Sequestrants
- 1.2.6 Others
- 1.3 By Indication
- 1.3.1 Hypercholesterolemia
- 1.3.2 Coronary Artery Disease
- 1.3.3 High Triglycerides
Chapter 2 Introduction
- 2.1 Report Objectives and Scope
- 2.2 Product Definition and Industry Terminology
- 2.3 Market Inclusions and Exclusions
- 2.4 Research Process
- 2.4.1 Primary Research and Expert Interviews
- 2.4.2 Secondary Research and Source Review
- 2.4.3 Top-Down and Bottom-Up Estimation
- 2.4.4 Data Triangulation and Verification
- 2.5 Market Size Measurement Basis
- 2.5.1 2025: USD 33.29 billion → 2035: USD 49.44 billion
- 2.6 Historical and Forecast Reference Periods
- 2.6.1 Historical Period: 2018-2025
- 2.6.2 Base Year: 2025
- 2.6.3 Forecast Period: 2025-2035
- 2.7 Research Assumptions and Limitations
Chapter 3 Executive Summary
- 3.1 Market Snapshot and Key Findings
- 3.2 Base-Year Market Size, 2025
- 3.3 Forecast Market Size, 2035
- 3.4 Revenue and Volume Growth Outlook
- 3.5 Key Demand and Supply Indicators
- 3.6 Leading Market Segments
- 3.7 Fastest-Growing Market Opportunities
- 3.8 Regional Performance Highlights
- 3.9 Technology and Industry Transformation
- 3.10 Competitive Landscape Summary
- 3.11 Analyst View and Strategic Implications
Chapter 4 Global Lipid-Lowering Drugs Market Trends and Developments
- 4.1 Historical Industry Development, 2018-2025
- 4.2 Recent Market Trends and Developments
- 4.3 Demand and Customer Behavior Trends
- 4.4 Technology and Product Innovation
- 4.5 Artificial Intelligence, Automation and Digitalization
- 4.6 Local Manufacturing and Supply Chain Realignment
- 4.7 Industry Partnerships, Mergers and Acquisitions
- 4.8 Sustainability and Circular Economy Developments
- 4.9 Government and Private Sector Investment Trends
- 4.10 Emerging Business Models and Commercialization
- 4.11 Industry Developments and Announcements
Chapter 5 Global Lipid-Lowering Drugs Market Production, Supply and Demand Analysis
- 5.1 Demand Trend and Consumption Analysis, 2018-2025
- 5.2 Demand Forecast, 2025-2035
- 5.3 Production and Output Trend, 2018-2025
- 5.4 Production and Output Forecast, 2025-2035
- 5.5 Installed Capacity and Capacity Utilization
- 5.6 Company-Wise Production Plants and Statistics
- 5.6.1 Installed Production Capacity
- 5.6.2 Actual Production
- 5.6.3 Planned Capacity and Expansion Targets
- 5.7 Supply Chain Structure and Procurement Trends
- 5.8 Supply-Demand Gap and Bottlenecks
- 5.9 Import Dependence and Sourcing Structure
- 5.10 Contract Manufacturing and Outsourcing
- 5.11 Regional Supply and Demand Concentration
Chapter 6 Global Lipid-Lowering Drugs Market Pricing Analysis
- 6.1 Pricing Structure and Measurement
- 6.2 Historical Pricing Trends, 2018-2025
- 6.3 Pricing Outlook, 2025-2035
- 6.4 Average Selling Price and Unit Economics
- 6.5 Pricing by Product and Market Segment
- 6.6 Geographic Pricing Differences
- 6.7 Key Input, Energy, Labor and Logistics Costs
- 6.8 Contract Pricing and Purchasing Models
- 6.9 Pricing Sensitivity and Competitive Positioning
- 6.10 Price, Margin and Profitability Implications
Chapter 7 Global Lipid-Lowering Drugs Market Dynamics
- 7.1 Market Growth Drivers
- 7.1.1 Demand-Side Drivers
- 7.1.2 Technology and Innovation Drivers
- 7.1.3 Infrastructure and Investment Drivers
- 7.1.4 Regulatory and Policy Drivers
- 7.2 Market Restraints
- 7.2.1 Cost and Affordability Constraints
- 7.2.2 Technology and Adoption Barriers
- 7.2.3 Supply Chain and Operational Constraints
- 7.3 Market Challenges
- 7.3.1 Competitive Pressure and Margin Erosion
- 7.3.2 Skills, Infrastructure and Implementation Gaps
- 7.4 Emerging Market Opportunities
- 7.5 Market Dynamics Impact and Time-Horizon Assessment
Chapter 8 Global Lipid-Lowering Drugs Value Chain Analysis
- 8.1 Industry Value Chain Overview
- 8.2 Upstream Suppliers and Critical Inputs
- 8.3 Technology and Component Providers
- 8.4 Manufacturing or Service Delivery
- 8.5 Distribution, Channel Partners and Integrators
- 8.6 Downstream Applications and End Users
- 8.7 Value Addition and Profit Pools
- 8.8 Vertical Integration and Outsourcing
- 8.9 Supplier Concentration and Risk
- 8.10 Supply Chain Localization and Resilience
Chapter 9 Global Lipid-Lowering Drugs Market Regulations and Policies
- 9.1 Relevant Laws, Standards and Compliance Frameworks
- 9.2 Product, Service, Safety and Quality Requirements
- 9.3 Government Policies, Incentives and Subsidies
- 9.4 Imports, Exports and Trade Barriers
- 9.5 Public Procurement and Local Content Requirements
- 9.6 Environmental and Sustainability Compliance
- 9.7 Upcoming Policy Changes and Market Implications
Chapter 10 Global Lipid-Lowering Drugs Market Hotspots and Opportunities
- 10.1 Market Opportunity Mapping and Growth Hotspots
- 10.2 High-Growth Applications and Customer Groups
- 10.3 Underserved Markets and White-Space Opportunities
- 10.4 Emerging Technology and Product Opportunities
- 10.5 New Capacity and Investment Hotspots
- 10.6 Market Entry and Expansion Opportunities
- 10.7 Distribution and Partnership Opportunities
- 10.8 Near-Term and Long-Term Commercial Potential
- 10.9 Opportunity Attractiveness and Execution Risks
Chapter 11 Global Lipid-Lowering Drugs Market Outlook, 2025-2035
- 11.1 Market Size and Analysis
- 11.1.1 Revenue (Market Measurement: 2025: USD 33.29 billion → 2035: USD 49.44 billion)
- 11.1.2 Market Volume and Quantity Sold
- 11.1.3 Historical Market Size, 2018-2025
- 11.1.4 Base-Year Market Size, 2025
- 11.2 Market Forecast, 2025-2035
- 11.2.1 Revenue Forecast to 2035
- 11.2.2 Volume Forecast to 2035
- 11.2.3 CAGR and Year-on-Year Growth
- 11.2.4 Incremental Revenue Opportunity
- 11.3 Forecast Assumptions and Scenario Analysis
- 11.3.1 Base-Case Forecast
- 11.3.2 Optimistic and Conservative Scenarios
- 11.3.3 Technology, Pricing and Policy Sensitivities
- 11.4 Market Attractiveness and Growth Outlook
Chapter 12 Global Lipid-Lowering Drugs Market Segmentation and Outlook
- 12.1 Segmentation Summary and Market Shares, 2025
- 12.2 Largest and Fastest-Growing Segments
- 12.3 By Drug - Market Size and Forecast, 2025-2035
- 12.3.1 Segment Definition and Scope
- 12.3.2 Historical Market Size, 2018-2025
- 12.3.3 Revenue Forecast, 2025-2035
- 12.3.4 Volume Forecast, 2025-2035
- 12.3.5 Base-Year Market Share, 2025
- 12.3.6 Segment CAGR and Growth Drivers
- 12.3.7 Subsegment Market Size and Forecast
- 12.3.7.1 Statins & Combination
- 12.3.7.2 PCSK9 Inhibitors
- 12.3.7.3 Cholesterol Absorption Inhibitors
- 12.3.7.4 Fibrates
- 12.3.7.5 Bile Acid Sequestrants
- 12.3.7.6 Others
- 12.3.8 Subsegment Pricing and Adoption Trends
- 12.3.9 Leading Suppliers and Competition
- 12.3.10 Regional Demand and Opportunities
- 12.4 By Indication - Market Size and Forecast, 2025-2035
- 12.4.1 Segment Definition and Scope
- 12.4.2 Historical Market Size, 2018-2025
- 12.4.3 Revenue Forecast, 2025-2035
- 12.4.4 Volume Forecast, 2025-2035
- 12.4.5 Base-Year Market Share, 2025
- 12.4.6 Segment CAGR and Growth Drivers
- 12.4.7 Subsegment Market Size and Forecast
- 12.4.7.1 Hypercholesterolemia
- 12.4.7.2 Coronary Artery Disease
- 12.4.7.3 High Triglycerides
- 12.4.8 Subsegment Pricing and Adoption Trends
- 12.4.9 Leading Suppliers and Competition
- 12.4.10 Regional Demand and Opportunities
- 12.5 Segment Growth Comparison
- 12.6 Segment Attractiveness and Priority Matrix
Chapter 13 Global Lipid-Lowering Drugs Geographic Market Outlook, 2025-2035
- 13.1 Regional Market Size and Share, 2025
- 13.2 Regional Market Forecast, 2025-2035
- 13.3 Regional Pricing, Production and Demand Differences
- 13.4 North America
- 13.4.1 United States
- 13.4.2 Canada
- 13.4.3 Mexico
- 13.5 Europe
- 13.5.1 Germany
- 13.5.2 France
- 13.5.3 Italy
- 13.5.4 United Kingdom
- 13.5.5 Spain
- 13.5.6 Poland
- 13.5.7 Russia
- 13.5.8 Netherlands
- 13.5.9 Belgium
- 13.5.10 Sweden
- 13.5.11 Denmark
- 13.5.12 Norway
- 13.5.13 Rest of Europe
- 13.6 Asia Pacific
- 13.6.1 China
- 13.6.2 India
- 13.6.3 Japan
- 13.6.4 South Korea
- 13.6.5 Thailand
- 13.6.6 Indonesia
- 13.6.7 Vietnam
- 13.6.8 Malaysia
- 13.6.9 Australia
- 13.6.10 Rest of Asia Pacific
- 13.7 Latin America
- 13.7.1 Brazil
- 13.7.2 Argentina
- 13.7.3 Colombia
- 13.7.4 Chile
- 13.7.5 Rest of Latin America
- 13.8 Middle East
- 13.8.1 Saudi Arabia
- 13.8.2 United Arab Emirates
- 13.8.3 Turkey
- 13.8.4 Israel
- 13.8.5 Iran
- 13.8.6 Rest of the Middle East
- 13.9 Africa
- 13.9.1 South Africa
- 13.9.2 Egypt
- 13.9.3 Nigeria
- 13.9.4 Morocco
- 13.9.5 Rest of Africa
- 13.10 Regional Investment, Policy and Supply Chain Differences
- 13.11 Regional Competitive Landscape
- 13.12 Geographic Growth Hotspots
Chapter 14 Global Lipid-Lowering Drugs Technology, Innovation and Sustainability Outlook
- 14.1 Technology Landscape and Maturity
- 14.2 Product, Process and Service Innovation
- 14.3 AI, Automation and Digital Tools in the Industry
- 14.4 Technology Adoption and Performance Benchmarking
- 14.5 Innovation Pipeline and R&D Investment
- 14.6 Patent and Intellectual Property Trends
- 14.7 Energy Efficiency and Resource Management
- 14.8 Sustainability, Recycling and Circularity
- 14.9 Technology Roadmap, 2025-2035
- 14.10 Risks of Obsolescence and Technology Substitution
Chapter 15 Global Lipid-Lowering Drugs Market Key Strategic Imperatives
- 15.1 Growth and Market Entry Priorities
- 15.2 High-Return Products and Segments
- 15.3 Pricing, Profitability and Cost Optimization
- 15.4 Technology Investment and Product Differentiation
- 15.5 Supply Chain Localization and Resilience
- 15.6 Distribution and Customer Acquisition
- 15.7 Partnership, Acquisition and Capacity Strategy
- 15.8 Regional Expansion Priorities
- 15.9 Short-, Medium- and Long-Term Actions
Chapter 16 Competition Outlook
- 16.1 Industry Competition Characteristics
- 16.2 Market Structure and Concentration
- 16.3 Market Share and Competitive Positioning, 2025
- 16.4 Company-Wise Revenue and Product Benchmarking
- 16.5 Production and Service Capacity Benchmarking
- 16.6 Technology, Pricing and Differentiation
- 16.7 Regional Footprint and Distribution Strength
- 16.8 Mergers, Acquisitions and Strategic Alliances
- 16.9 New Entrants and Competitive Threats
- 16.10 Porter's Five Forces and Industry Attractiveness
- 16.11 Competitive Outlook, 2025-2035
Chapter 17 Company Profiles
- 17.1 Company Coverage and Selection Criteria
- 17.2 Sanofi
- 17.2.1 Business Description
- 17.2.2 Company Ownership and Geographic Presence
- 17.2.3 Product and Service Portfolio
- 17.2.4 Manufacturing and Operating Footprint
- 17.2.5 Production Capacity and Expansion Plans
- 17.2.6 Financial Performance and Investment
- 17.2.7 Market Share and Competitive Position
- 17.2.8 Technology and Innovation Capabilities
- 17.2.9 Strategic Alliances or Partnerships
- 17.2.10 Recent Developments
- 17.2.11 Growth Strategy and Outlook
- 17.3 Pfizer, Inc.
- 17.4 GlaxoSmithKline plc
- 17.5 Novartis AG
- 17.6 Merck & Co., Inc.
- 17.7 Amgen Inc.
- 17.8 Takeda Pharmaceutical Company Limited
- 17.9 Sun Pharmaceutical Industries Ltd.
- 17.10 AbbVie, Inc.
- 17.11 Viatris (Mylan N.V.)
- 17.12 AstraZeneca PLC
- 17.13 Dr. Reddy's Laboratories Ltd.
- 17.14 Other Relevant Market Participants
Note: Every listed company is profiled on the structure shown under the first company. The company list is preliminary and may change based on research findings, market developments, data availability and client requirements.
Chapter 18 Disclaimer
- 18.1 Research and Forecast Disclaimer
- 18.2 Data Source and Estimation Limitations
Note: The depth of individual sections depends on data availability for this market. Volume, capacity, trade and other unit-based metrics are included where applicable.

