
Chronic cases drive pouchitis treatment spending
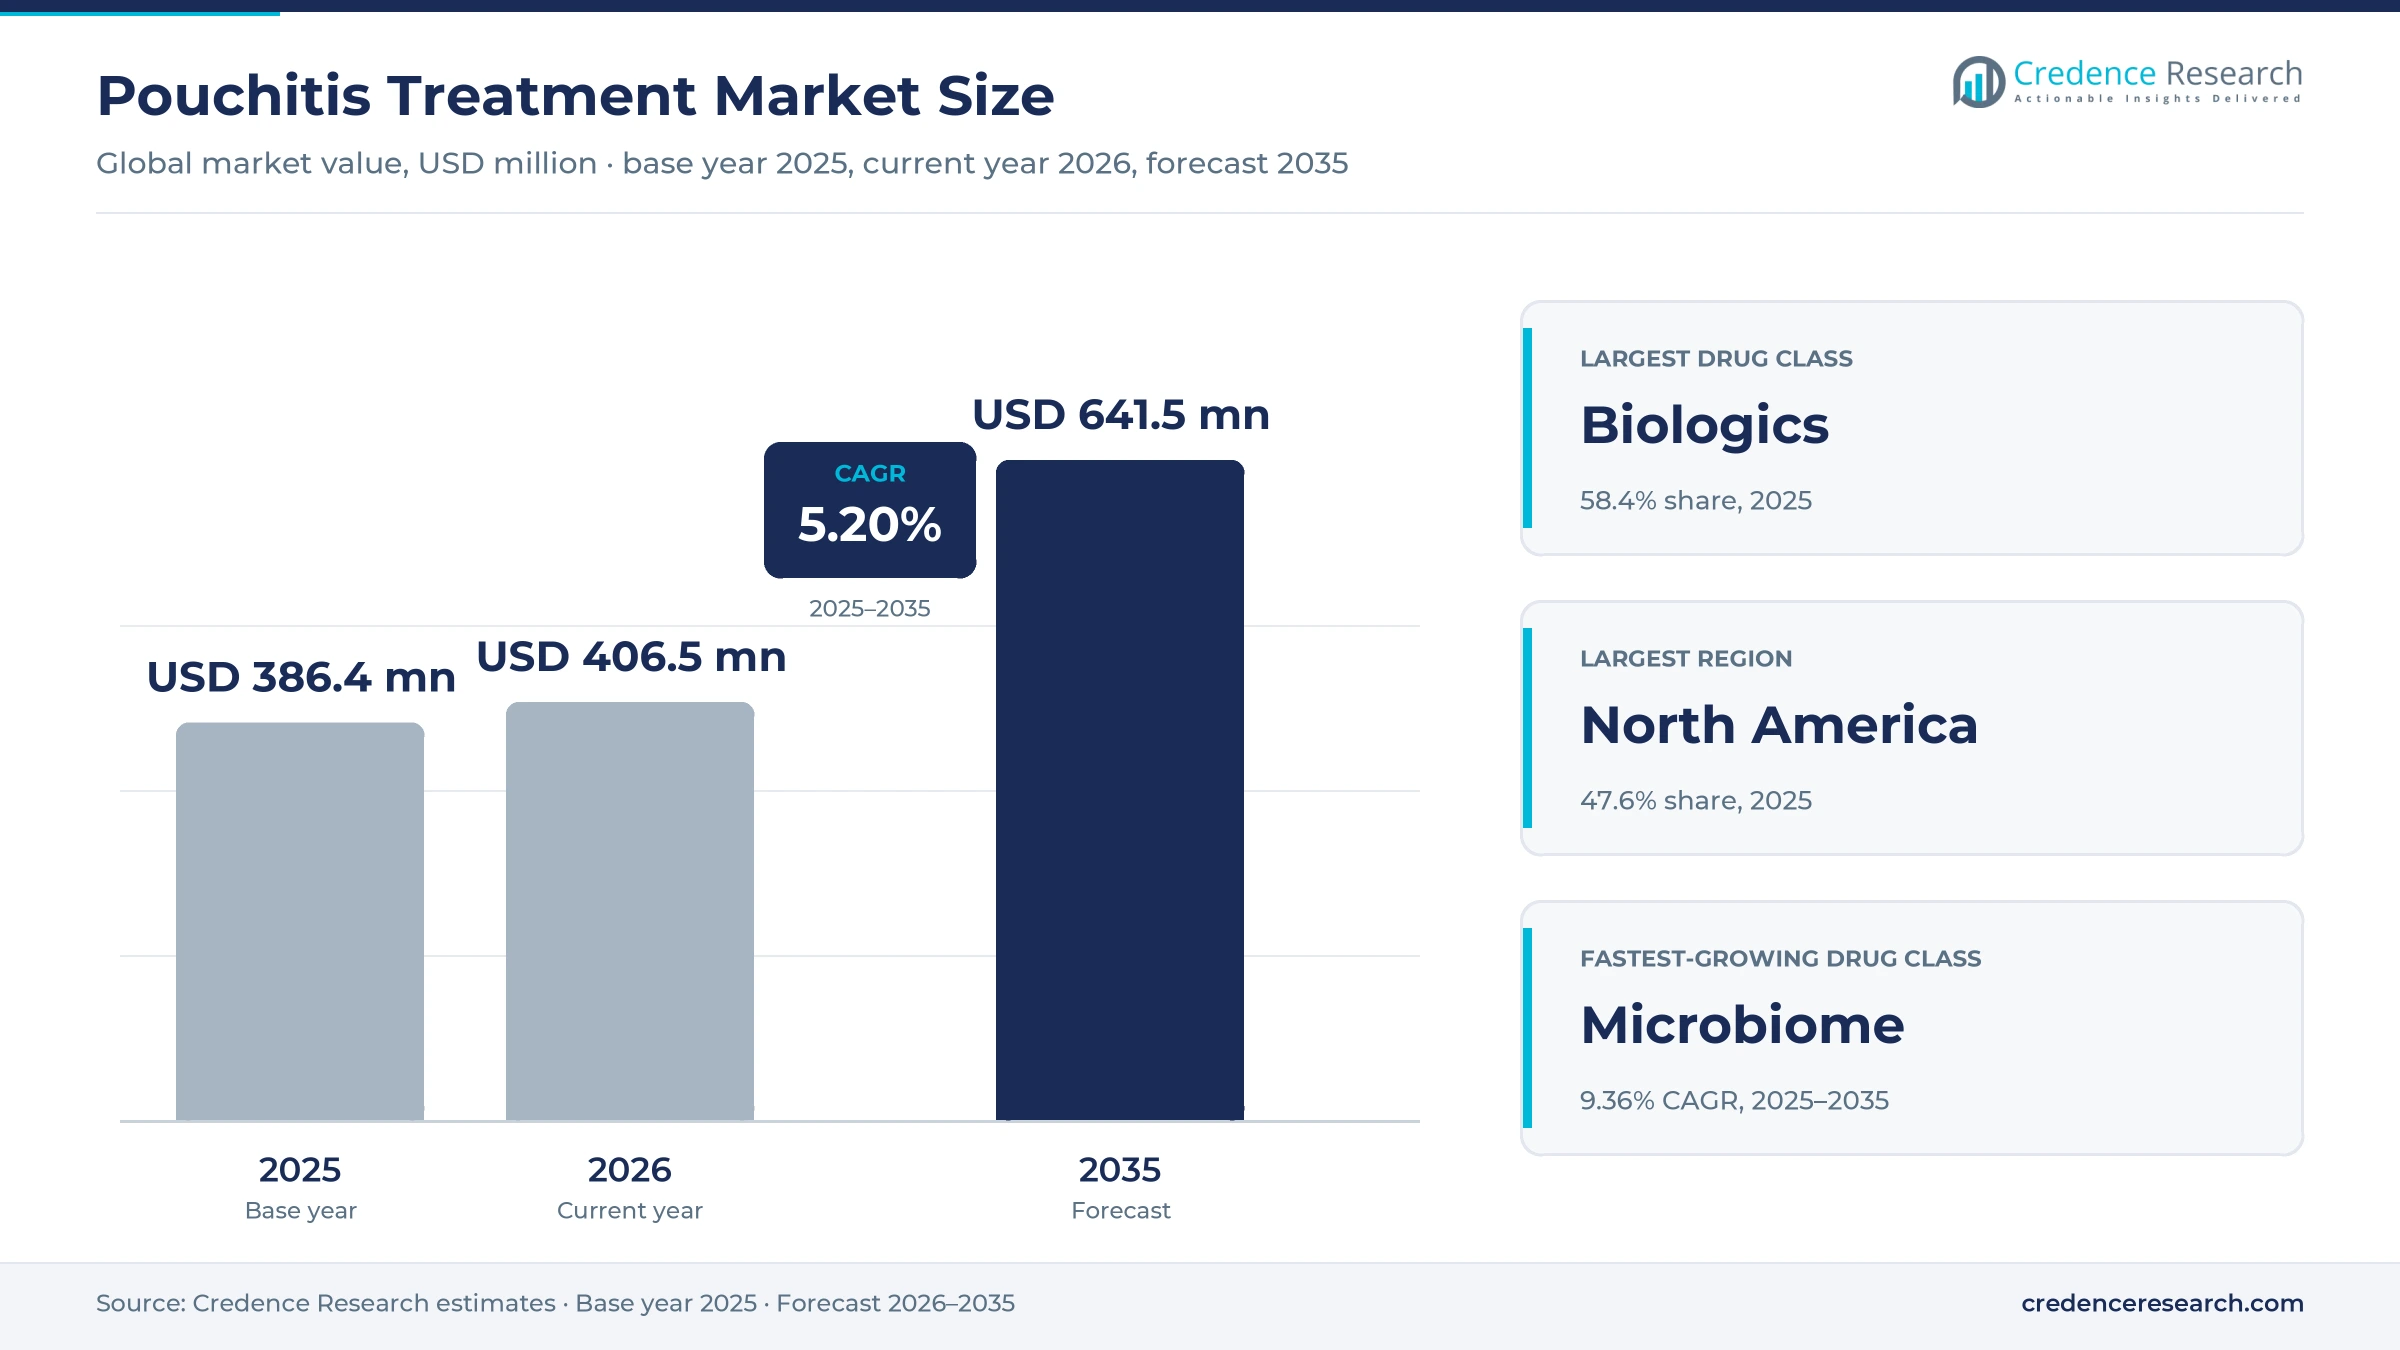
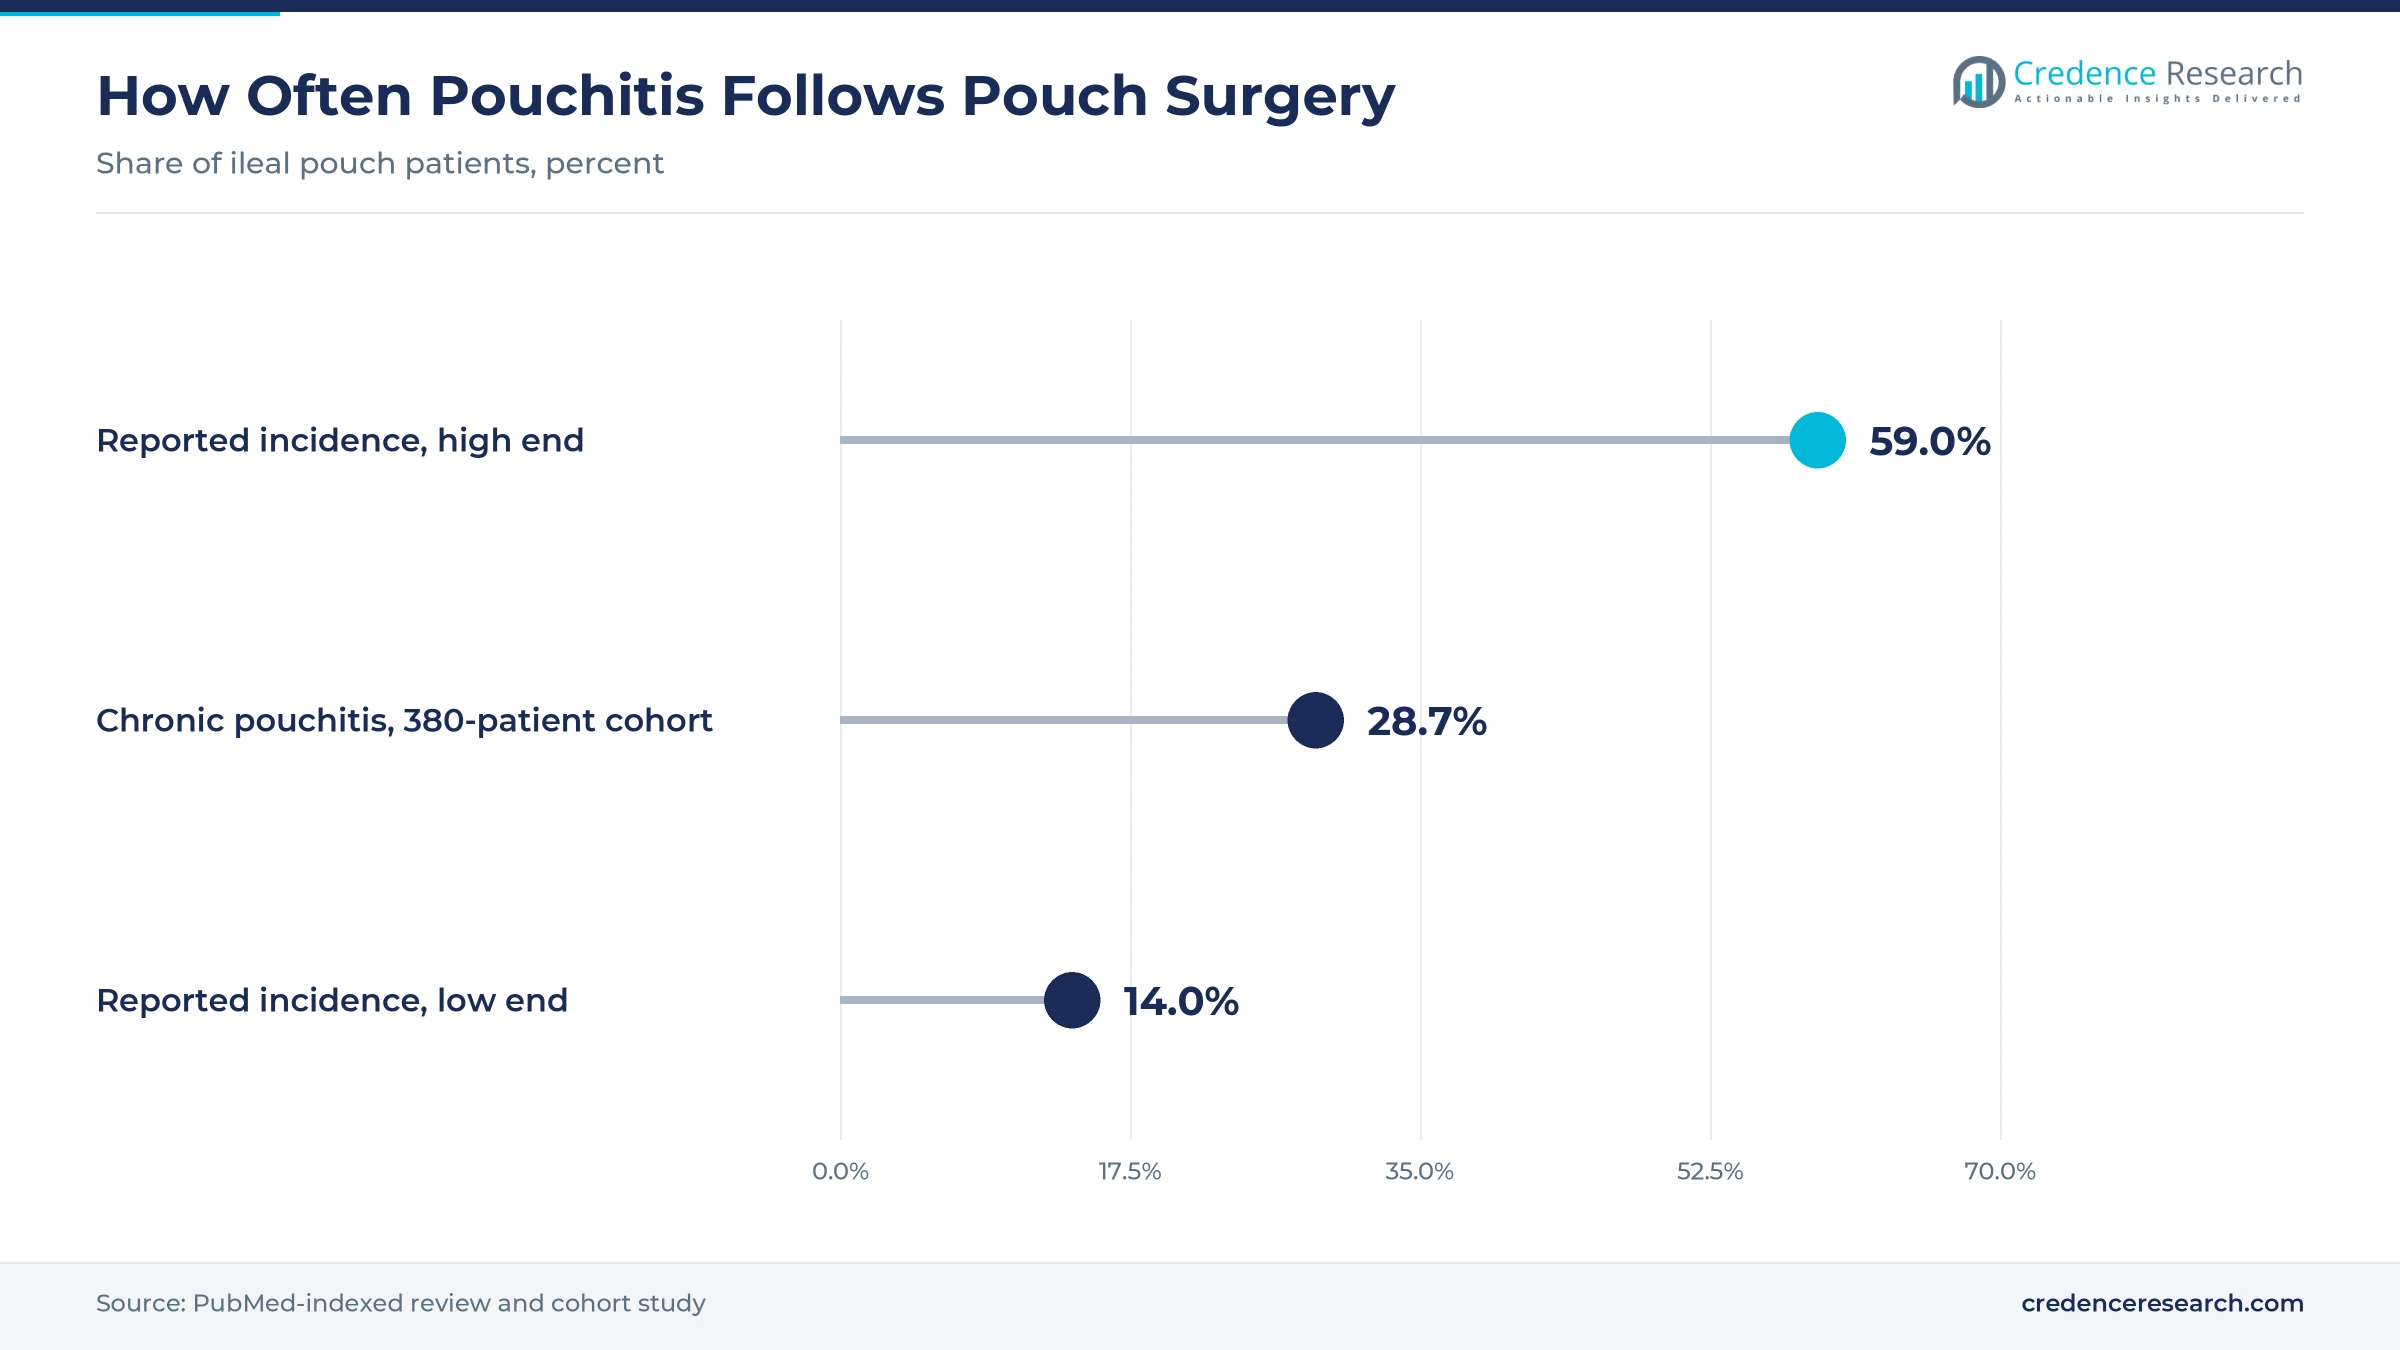
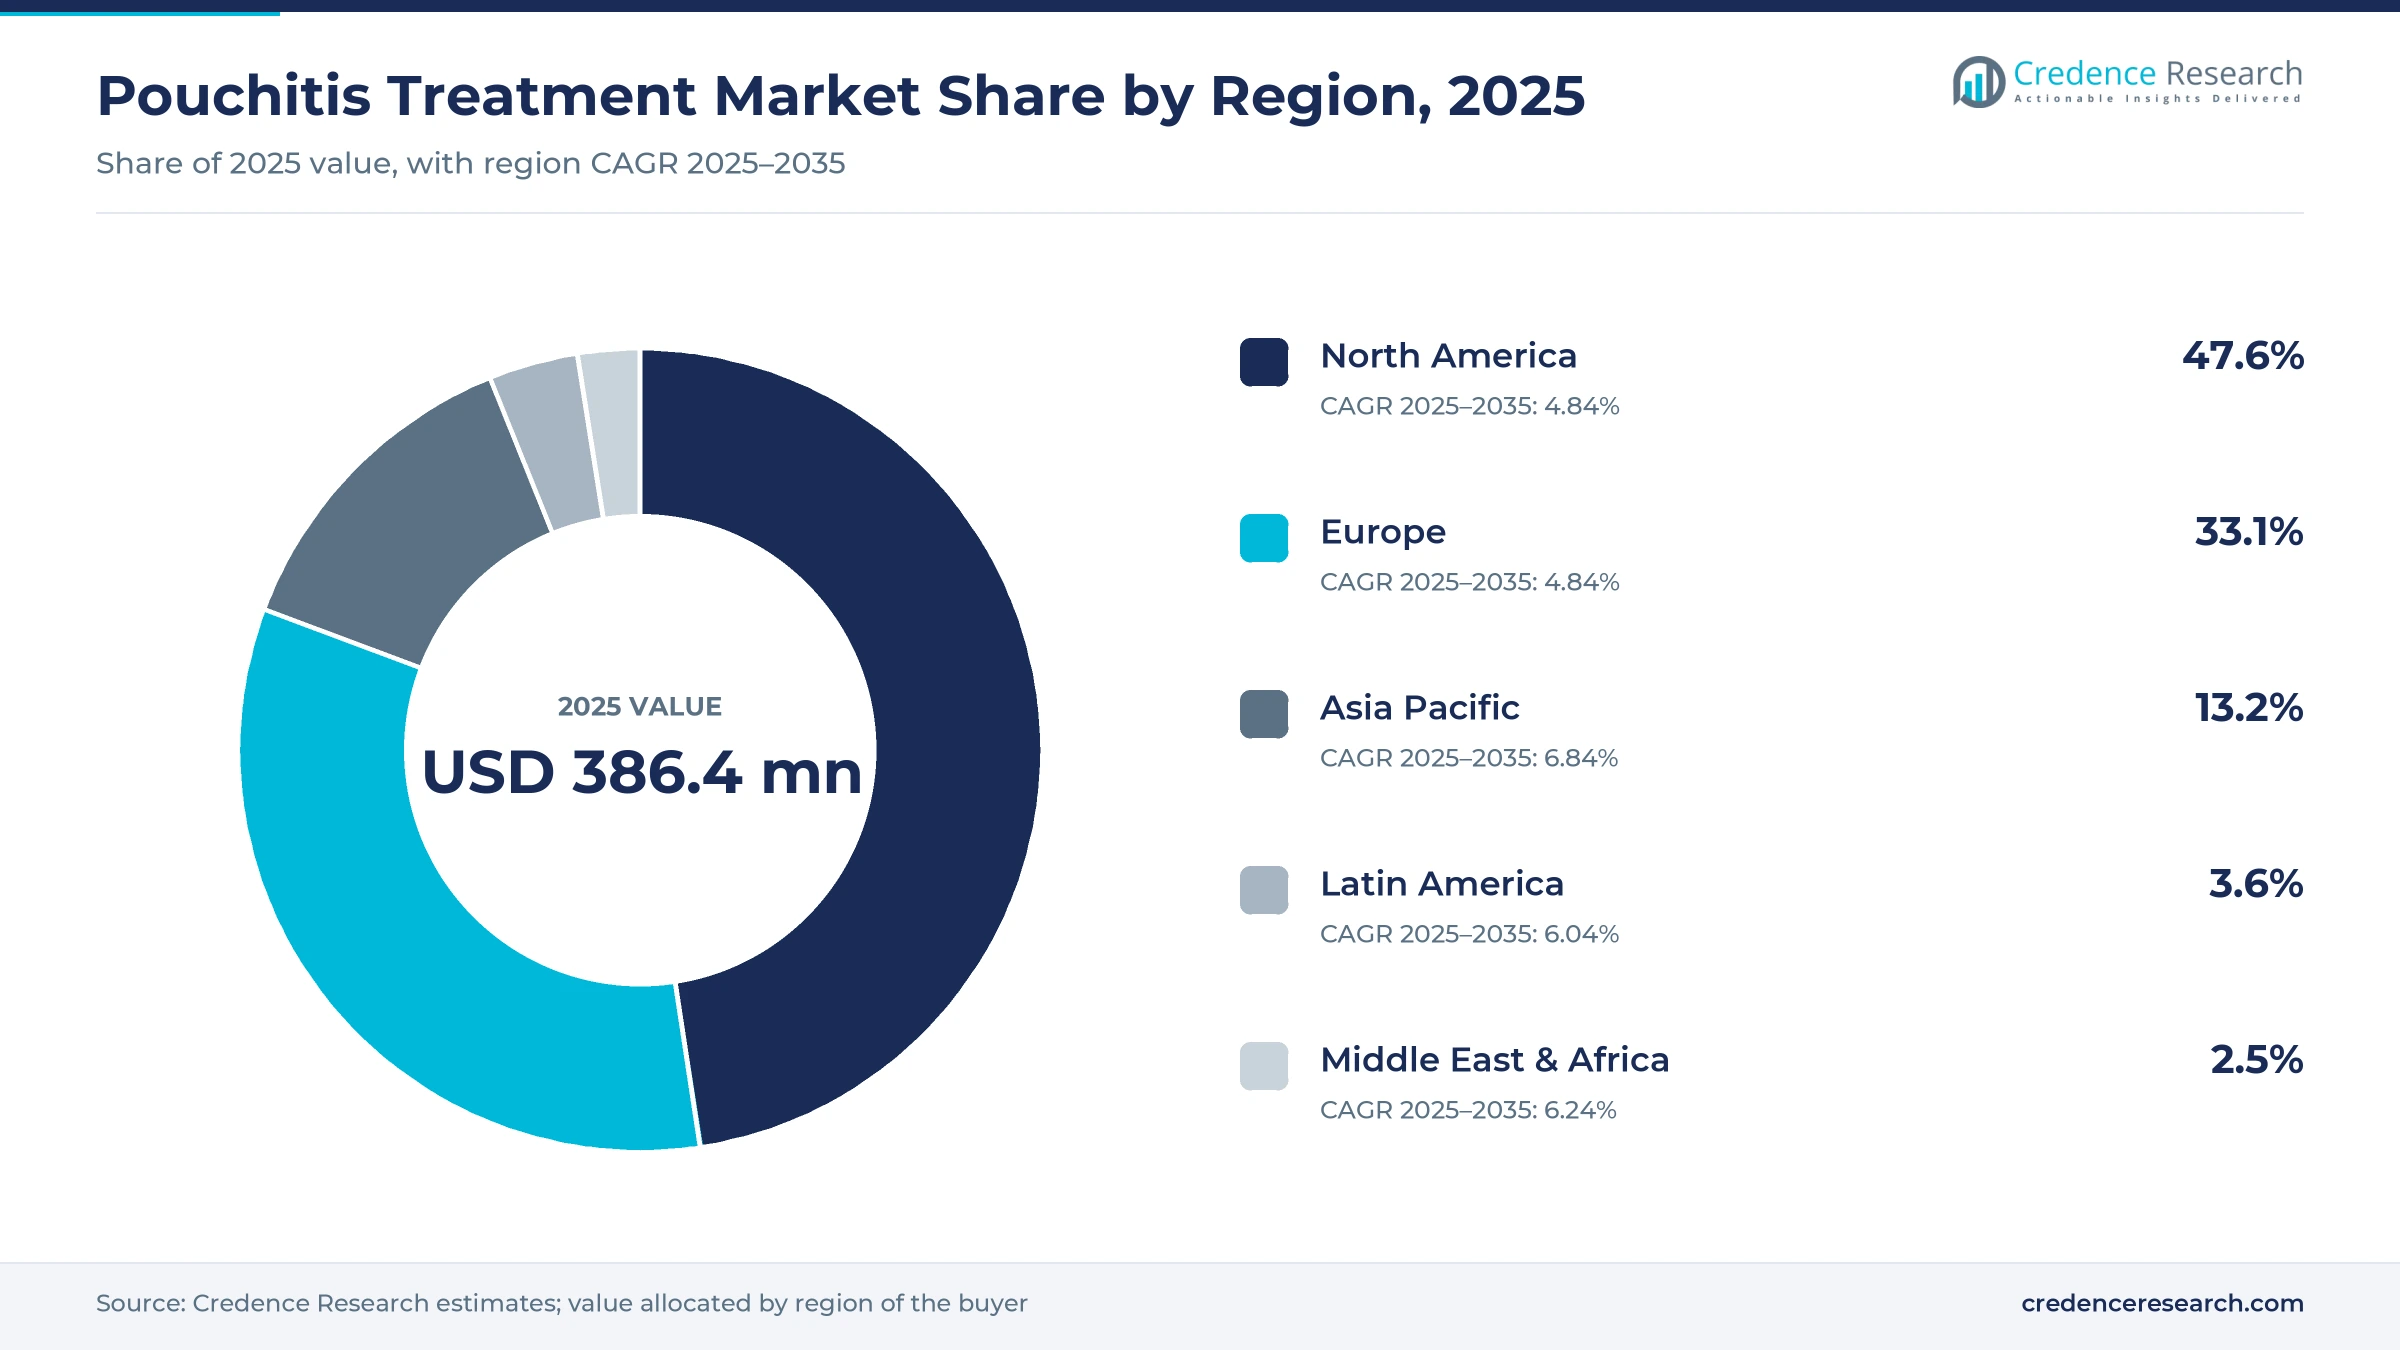
The pouchitis treatment market was valued at USD 386.4 million in 2025 and is projected to increase from USD 406.5 million in 2026 to USD 641.5 million by 2035, registering a CAGR of 5.20% during 2025–2035. Demand comes from three sources, as the pool of people living with an ileal pouch after surgery for ulcerative colitis is growing, the chronic share of pouchitis needs years of maintenance therapy, and biologics see wider use once antibiotics stop working. Reported incidence ranges from 14% to 59% of pouch patients, so even a small surgical population generates steady treatment demand. North America held the largest regional share, 47.6% in 2025, because U.S. biologic prices are the highest anywhere, while Asia Pacific is the fastest-growing region at 6.84% a year. The key regulatory change was the European Commission's February 2022 approval of intravenous vedolizumab for chronic pouchitis, still the only biologic with a pouchitis label.
What counts as pouchitis treatment spending?
Pouchitis is inflammation of the ileal pouch that surgeons build after removing the colon and rectum, most often in people with ulcerative colitis. Treatment follows clear steps, starting with a 2-week antibiotic course for an acute flare, while rotating antibiotics or multi-strain probiotics serve patients who relapse and biologics or targeted small molecules treat chronic cases that do not respond. Spending comes mainly from hospital and specialty pharmacy budgets, with biologic access set by payers.
The market includes biologics and targeted small molecules, antibiotics such as ciprofloxacin, metronidazole and rifaximin, probiotics, corticosteroids and 5-ASA, and fecal microbiota transfer and live biotherapeutics. It excludes pouch surgery and revision, endoscopy and other diagnostic costs, and ostomy products for patients whose pouch fails. Those exclusions keep the estimate focused on recurring drug spending rather than one-time surgical costs.
Pouchitis Treatment Market Insights
- The pouchitis treatment market is projected to grow from USD 406.5 million in 2026 to USD 641.5 million by 2035, a 5.20% CAGR, as chronic cases move to maintenance therapy.
- North America held 47.6% of 2025 value, the largest regional share, because U.S. biologic prices are the highest even without a U.S. pouchitis label.
- Biologics and targeted small molecules accounted for 58.4% of 2025 value, the largest drug class, because maintenance therapy costs far more than antibiotic courses.
- Treatment is shifting from repeated antibiotics to earlier biologic use, and interleukin-23 drugs such as mirikizumab entered pouch-specific trials in 2025.
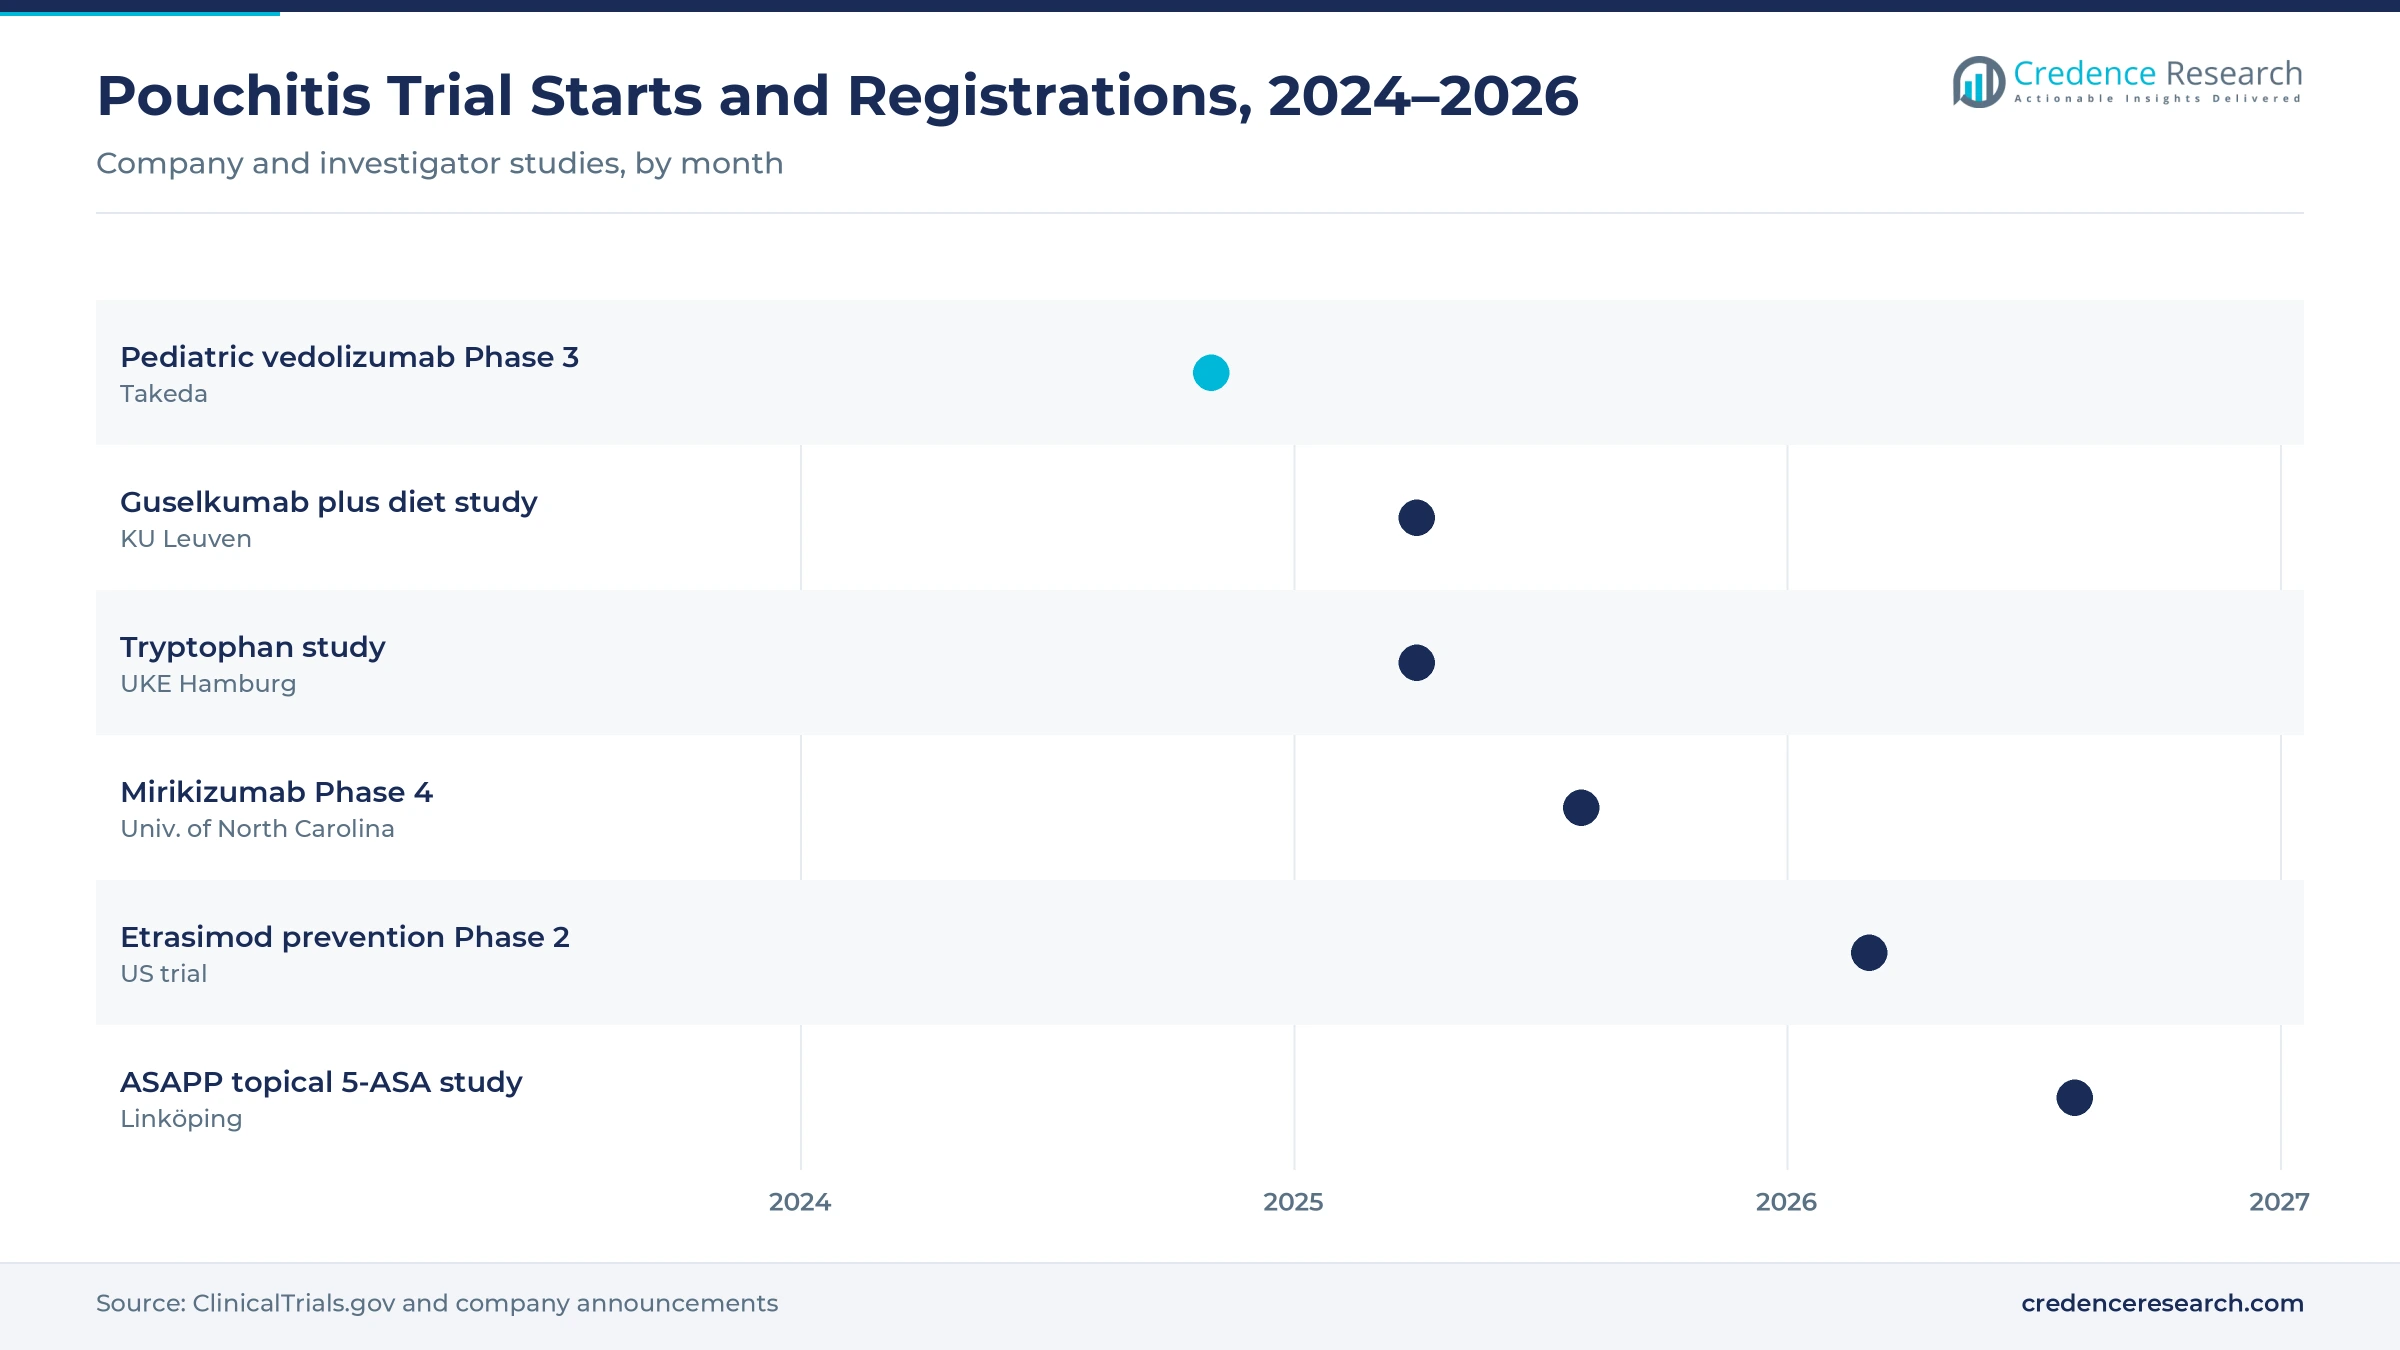
- Takeda holds the only EU-labeled pouchitis biologic and began a pediatric Phase 3 study in November 2024; microbiome therapies grow fastest at 9.36% a year.
Biologics lead while microbiome therapies grow fastest
Biologics lead by drug class while microbiome therapies grow fastest
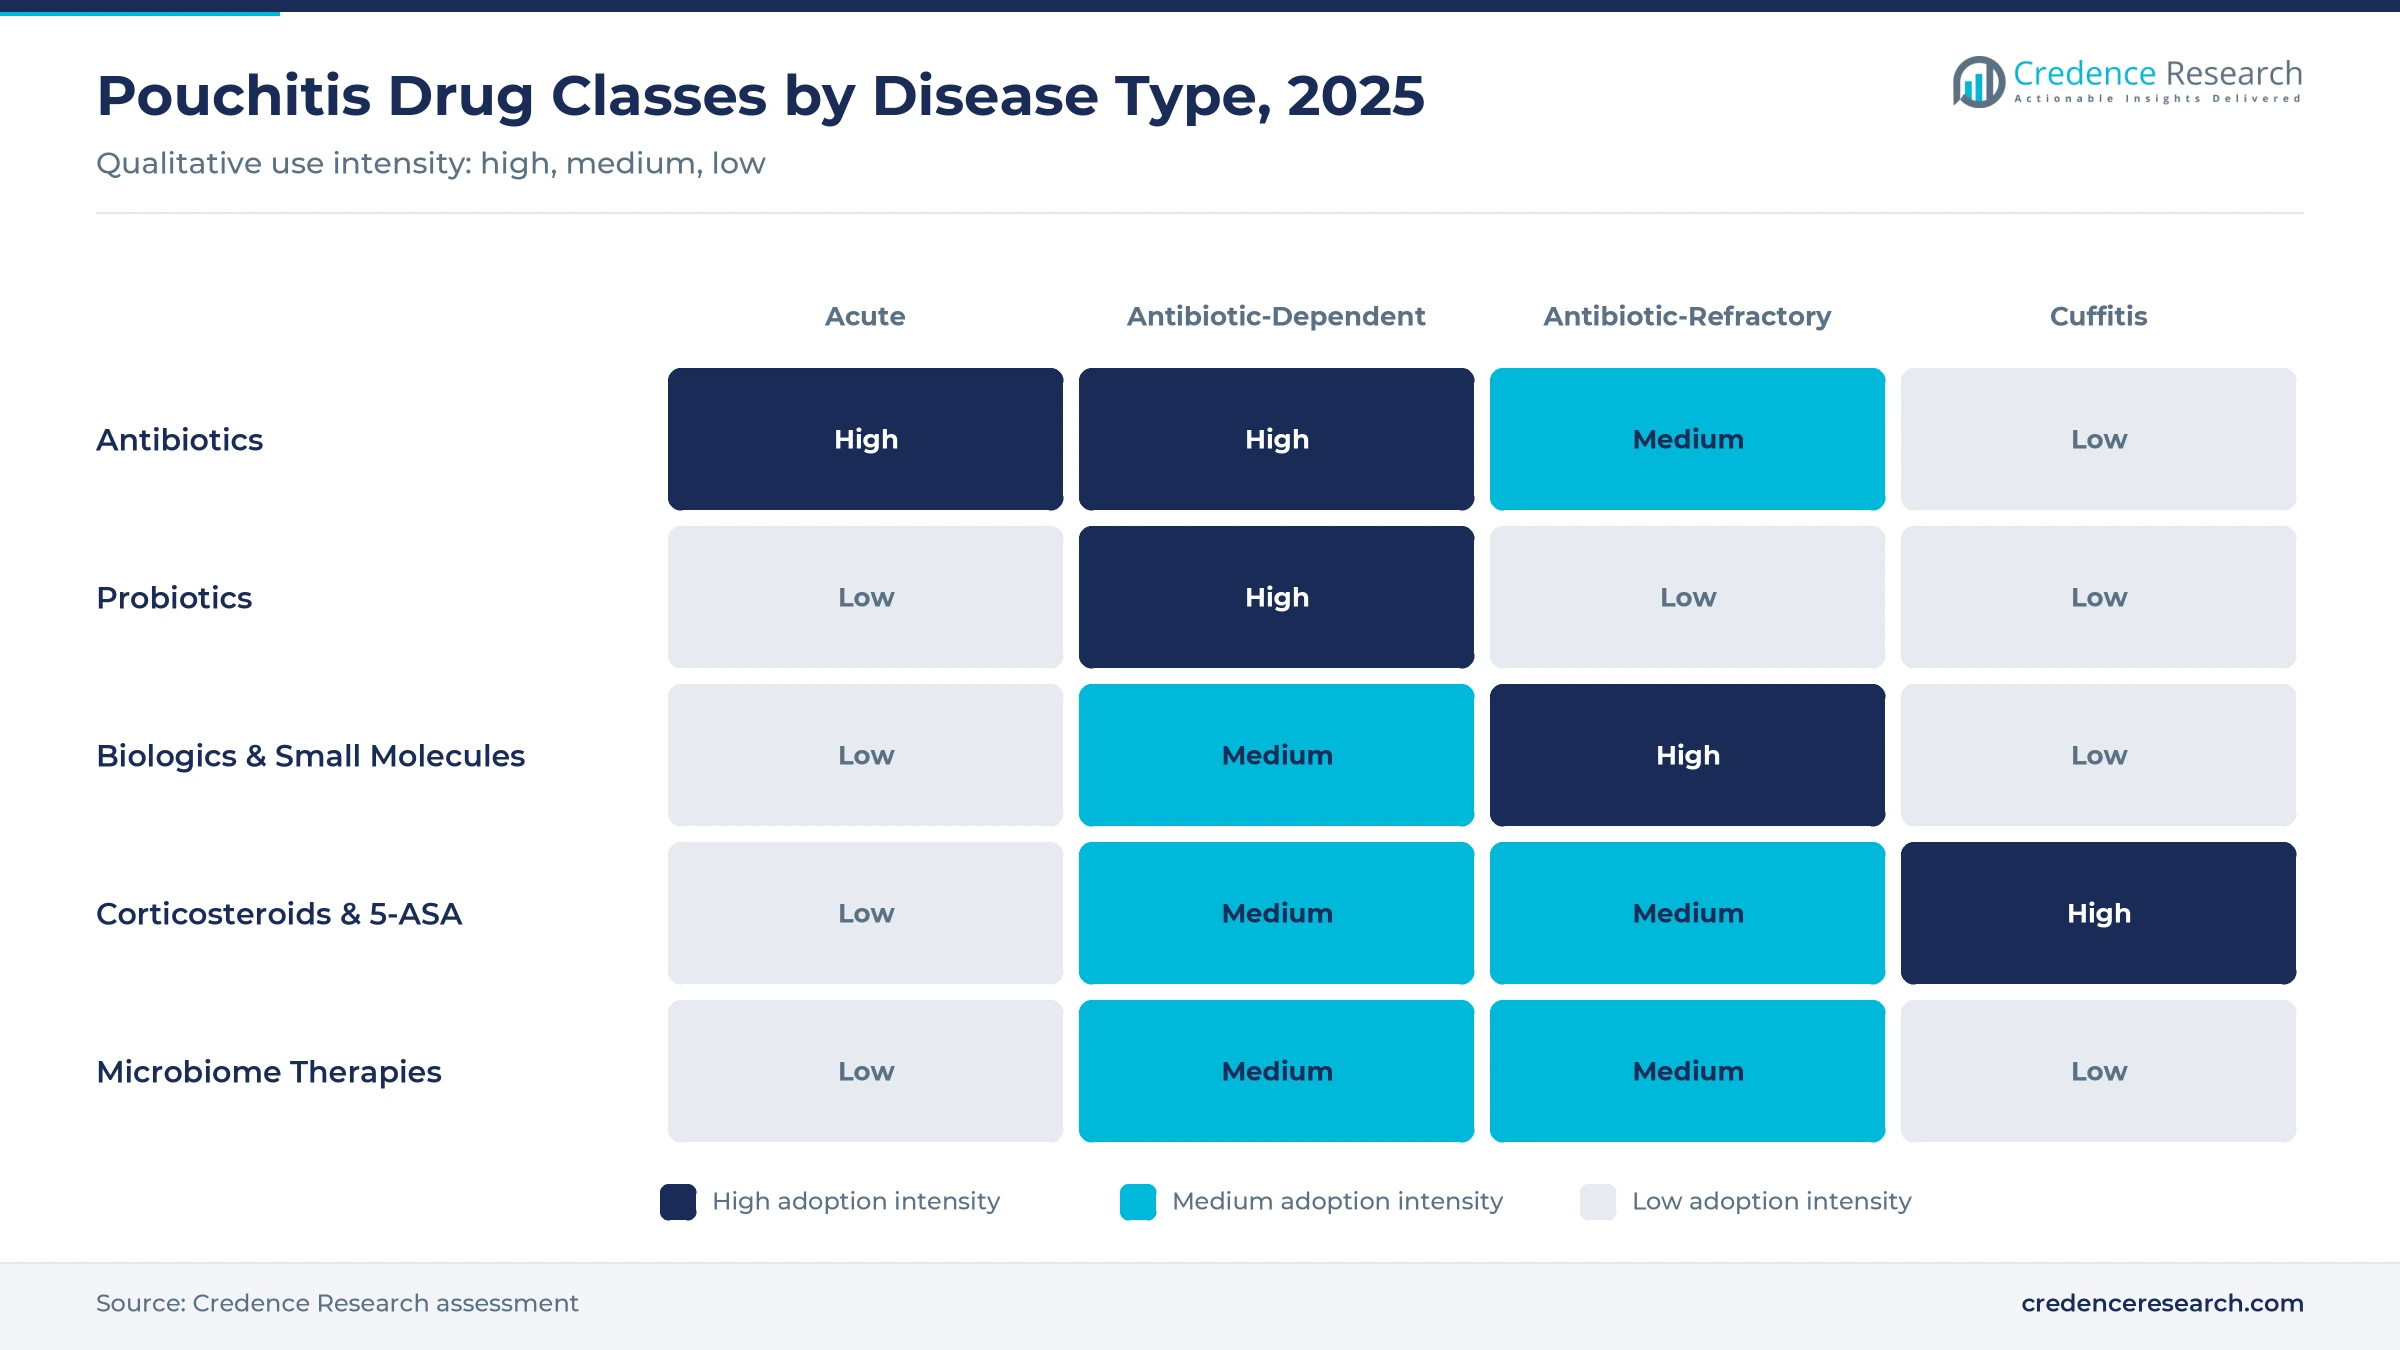
Based on drug class, the market is categorized into biologics and targeted small molecules, antibiotics, probiotics, corticosteroids and 5-ASA, and microbiome and other therapies. Biologics and targeted small molecules led with 58.4% of 2025 value. Only a minority of patients take them, but a year of vedolizumab or an off-label anti-TNF drug costs many times a course of generic antibiotics. Microbiome and other therapies grow fastest at 9.36% a year from a small base, as fecal microbiota transfer and live biotherapeutics move through trials.
Antibiotic-refractory pouchitis leads by disease type and grows fastest
Based on disease type, the market is categorized into acute pouchitis, chronic antibiotic-dependent pouchitis and chronic antibiotic-refractory pouchitis. Chronic antibiotic-refractory pouchitis led with 45.5% of 2025 value and is also the fastest-growing type at 6.00% a year, because these patients need long-term advanced therapy. Acute cases are the most common but the cheapest to treat, since most clear with a 2-week antibiotic course, and antibiotic-dependent patients rely mainly on rotating antibiotics or probiotics.
| Segment Group | Leading Sub-segment | Share, 2025 | Fastest-growing Sub-segment | CAGR, 2025–2035 |
|---|---|---|---|---|
| By Drug Class | Biologics & Targeted Small Molecules | 58.4% | Microbiome & Other Therapies | 9.36% |
| By Disease Type | Chronic Antibiotic-Refractory Pouchitis | 45.5% | Chronic Antibiotic-Refractory Pouchitis | 6.00% |
Request a Free Sample
Fill in your details and we'll send you a free sample report.
- Sample data tables & charts
- Research methodology
Chronic cases, an EU label and new trials push spending
Chronic pouchitis turns short antibiotic courses into years of therapy
Chronic pouchitis is the main driver of treatment spending, because that is where costs accumulate. A review indexed on PubMed puts reported incidence at 14% to 59% of pouch patients, and in a community cohort of 380 patients, 28.7% developed chronic pouchitis during long-term follow-up. These patients need maintenance therapy for years rather than a 2-week antibiotic course, and many move on to biologics. Chronic antibiotic-refractory pouchitis is the largest disease type at 45.5% of 2025 value, and the effect builds through 2035.
The EU vedolizumab label gives payers a reason to fund biologics
Before 2022, no drug was approved for chronic pouchitis in Europe, and doctors used biologics off-label. In February 2022, the European Commission approved intravenous vedolizumab for adults with moderately to severely active chronic pouchitis after an inadequate response to antibiotics, as Takeda announced. In the EARNEST trial, 31.4% of patients on vedolizumab reached clinical remission at week 14, against 9.8% on placebo. The label lets payers in Germany, France and other EU markets fund a biologic without case-by-case appeals.
A growing pouch population expands the number of patients at risk
The patient pool grows slowly but steadily, because ulcerative colitis rates are rising in Asia, Latin America and the Middle East, and a share of those patients will need colectomy and an ileal pouch. Pouch patients also live with the pouch for decades, so the number at risk keeps building even where surgery rates are flat. The effect is long term and strongest in Asia Pacific, the fastest-growing region.
New inflammatory bowel disease drugs enter pouch-specific trials
Every new ulcerative colitis drug is a candidate for pouchitis, because pouch inflammation behaves like ulcerative colitis in the small bowel. In August 2025, the University of North Carolina launched a Phase 4 study of intravenous and subcutaneous mirikizumab in chronic inflammatory conditions of the pouch, listed on ClinicalTrials.gov. Investigator studies of guselkumab and etrasimod are also registered, and each new data set widens the options payers are asked to fund. Credence Research expects the commercial effect to come mainly after 2028.
Earlier biologic use and IL-23 trials reshape pouch care
Treatment shifts earlier from antibiotics to advanced therapy
Doctors are moving patients with relapsing pouchitis off long-term antibiotics sooner. Repeated courses breed resistance and side effects, and guidelines now support biologics once a patient is antibiotic-dependent or refractory. The shift moves value from low-cost generics toward biologics every year, which is why biologics hold 58.4% of 2025 value. Antibiotics remain first-line for almost every acute episode, so volume stays with generics while value moves to specialty drugs dispensed through hospital pharmacies.
Interleukin-23 inhibitors follow vedolizumab into the pouch
After vedolizumab, the next drug class under study is the interleukin-23 inhibitors already used in ulcerative colitis. Mirikizumab started a Phase 4 study in pouch inflammation in 2025, and a KU Leuven study announced in April 2025 combines guselkumab with a dietary program. Biosimilar ustekinumab reached the U.S. market in 2025, lowering the cost of an older IL-12/23 option. Credence Research expects IL-23 drugs to take a growing slice of biologic spending after 2028 as pouch data mature.
Microbiome therapies moving from theory to trials open an opportunity
Pouchitis responds to antibiotics, which points to bacteria as a cause and makes the pouch a natural test bed for fecal microbiota transfer and live biotherapeutic products. Microbiome and other therapies are the fastest-growing drug class at 9.36% a year. Exegi Pharma, maker of the Visbiome multi-strain probiotic, is testing its EXE-346 live biotherapeutic in pouch patients. Developers that show consistent strain counts and durable remission could win maintenance patients now managed with antibiotics.
Preventing pouchitis after pouch surgery offers an opportunity
Trials now test whether pouchitis can be prevented rather than treated. A Phase 2 study of etrasimod for pouchitis prevention was registered in the United States in March 2026, and Linköping University Hospital registered the ASAPP study of topical 5-ASA after pouch surgery in August 2026. Rifaximin from Bausch Health's Salix unit is also under study for preventing recurrent pouchitis. If any approach succeeds, treatment would start earlier and reach more of the patients who undergo pouch surgery each year.
Small trials, a U.S. label gap and biosimilars curb revenue
Small, slow trials keep most advanced therapy off-label
Pouchitis is a rare condition, so trials are small and slow to recruit. Many current studies enroll 16 to 40 patients, too few to support a new label on their own. Drug makers therefore see little return on pouch-specific programs, and most advanced therapy stays off-label, with payers asking for proof of failed antibiotics first. Multicenter registries, shared endpoints and pediatric extension studies such as Takeda's Phase 3 program help build the evidence base faster for drugs already in use.
No U.S. pouchitis label means prior-authorization battles
No drug carries a U.S. label for chronic pouchitis, so American gastroenterologists use vedolizumab, anti-TNF agents and ustekinumab off-label, which means prior-authorization appeals, treatment delays and uneven access across insurers. The gap holds North America's growth below the global market rate. The first company to win a U.S. label would gain a clear edge with payers, and specialist centers limit delays with standard records of failed antibiotic courses.
Biosimilars cut spending per treated patient
Biosimilar infliximab and adalimumab have already cut the price of anti-TNF therapy, biosimilar ustekinumab reached the U.S. market in 2025, and vedolizumab faces biosimilar competition later in the forecast. Lower prices widen access for patients and payers but reduce revenue per treated patient for originator companies, which is why Credence Research keeps biologic growth close to the market average. Originators respond with subcutaneous dosing, pediatric data and pouch-specific evidence that support continued use.
Antibiotic resistance erodes the cheapest first-line option
Long-term antibiotic use selects resistant bacteria and raises the risk of Clostridioides difficile infection. Patients with antibiotic-dependent pouchitis, who may take ciprofloxacin or metronidazole for months, are most exposed. Resistance pushes some patients toward costlier advanced therapy faster, but it leaves others without a cheap first-line option, especially where biologic access is limited. Mitigation comes from rotating antibiotics, probiotic maintenance and earlier step-up for patients who relapse within weeks of stopping treatment.
North America leads on price as Asia Pacific adds patients
| Region | Share, 2025 | CAGR, 2025–2035 |
|---|---|---|
| North America | 47.6% | 4.84% |
| Europe | 33.1% | 4.84% |
| Asia Pacific | 13.2% | 6.84% |
| Latin America | 3.6% | 6.04% |
| Middle East & Africa | 2.5% | 6.24% |
North America's high biologic prices outweigh the missing U.S. label
North America held 47.6% of 2025 value and grows at 4.84% a year. The United States has a large population of pouch patients and the highest biologic prices, which explains its lead. Without a U.S. pouchitis label, most advanced therapy is off-label and depends on payer approval, so growth tracks prior-authorization policy as much as patient numbers. Canada follows similar treatment patterns, with access set through provincial formularies. A first U.S. label, if one is granted, would be the largest upside for the region.
Europe is the only region with an approved pouchitis biologic
Europe held 33.1% of 2025 value and grows at 4.84% a year. It is the only region with an approved biologic for chronic pouchitis, and the Entyvio product information published by the European Medicines Agency lists the indication. Germany, the United Kingdom, France, Italy and the Nordic countries run large pouch surgery programs and specialist IBD centers. Academic sites such as KU Leuven in Belgium, University Medical Center Hamburg-Eppendorf and Linköping University Hospital in Sweden lead most investigator trials.
Asia Pacific grows fastest as ulcerative colitis rates rise
Asia Pacific held 13.2% of 2025 value and is the fastest-growing region at 6.84% a year. Japan has the largest pouch population in the region and broad biologic access. Rising ulcerative colitis rates in China, South Korea and India add new pouch patients each year, and Australia follows European treatment patterns. Growth comes from a larger treated population rather than higher prices, so suppliers with affordable biologics and biosimilars are best placed to win new patients.
Latin America and Middle East & Africa concentrate care in referral hospitals
Latin America held 3.6% of 2025 value and grows at 6.04% a year. Brazil, Mexico and Argentina lead, with pouch surgery concentrated in large public and private referral hospitals and biologic access varying widely by payer. The Middle East & Africa held 2.5% and grows at 6.24% a year. Saudi Arabia, Israel, the United Arab Emirates and South Africa account for most specialist IBD care, and Gulf health systems fund biologics more readily than most of Africa.
Five pouchitis trial starts since November 2024
| Development | Status and market relevance |
|---|---|
| In August 2026, Linköping University Hospital registered the ASAPP study of topical 5-ASA to prevent pouchitis after pouch surgery. | Registered. Tests prevention with a low-cost therapy. |
| In March 2026, a U.S. Phase 2 trial of etrasimod for pouchitis prevention was announced on ClinicalTrials.gov. | Registered. Brings an oral S1P modulator into prevention. |
| In August 2025, the University of North Carolina launched a Phase 4 study of intravenous and subcutaneous mirikizumab in chronic inflammatory conditions of the pouch. | Launched. First IL-23 study dedicated to the pouch. |
| In April 2025, KU Leuven announced a study combining guselkumab with a dietary program in pouchitis. | Announced. Tests a second IL-23 drug alongside diet. |
| In November 2024, Takeda launched a Phase 3 study of vedolizumab in children and teenagers with pouchitis. | Launched. Extends the only labeled biologic toward younger patients. |
Gut-selective biologics, IL-23 drugs and microbiome products
- Diagnosis by pouchoscopy with biopsy and diagnostic scores separates pouchitis from cuffitis, irritable pouch syndrome and Crohn's-like disease of the pouch, so fewer patients cycle through repeated antibiotic courses.
- Gut-selective biologics are led by vedolizumab, which blocks immune-cell traffic to the gut and remains the benchmark, with 31.4% clinical remission at week 14 in the EARNEST trial.
- IL-23 inhibitors such as mirikizumab and guselkumab, already used in ulcerative colitis, are the next drug class under pouch-specific study.
- Oral small molecules such as etrasimod, an oral S1P receptor modulator, are being tested for prevention, which could bring advanced therapy to patients before chronic disease sets in.
- Microbiome products such as fecal microbiota transfer and defined live biotherapeutics like EXE-346 target the bacterial cause of pouch inflammation.
Need a Custom Version of This Report?
Tailor the scope, geography, or segments to your exact requirements.
- Custom geography or segment scope
- Direct access to our analyst team
Takeda holds the only label as rivals gather pouch data
Competition splits into three groups, and biologic and immunology companies hold most of the value, led by Takeda Pharmaceutical, whose Entyvio is the only biologic carrying a pouchitis label. Johnson & Johnson, Eli Lilly, AbbVie and Pfizer supply ustekinumab, guselkumab, mirikizumab, adalimumab, upadacitinib, risankizumab, infliximab and etrasimod, which are used off-label or studied in the pouch. Antibiotic suppliers, including Bausch Health through Salix and generic makers such as Teva Pharmaceutical, serve acute episodes at low prices. Probiotic and microbiome developers, led by Exegi Pharma, target maintenance and prevention. Entry barriers are high for biologics, which need clinical data and payer acceptance, but low for generics. Pouch evidence now comes mostly from investigator trials rather than company-sponsored programs. No company reports pouchitis sales separately, so no share ranking is given.
Pouchitis treatment suppliers and their roles
| Company | Type | Role in the market |
|---|---|---|
| Takeda Pharmaceutical | Biologic maker | Entyvio (vedolizumab), EU-labeled for chronic pouchitis; pediatric Phase 3 study |
| Johnson & Johnson | Immunology company | Ustekinumab and guselkumab, used off-label or under investigator study |
| Eli Lilly | Immunology company | Mirikizumab, studied in an investigator-led Phase 4 pouch trial |
| AbbVie | Immunology company | Adalimumab, upadacitinib and risankizumab used off-label; pouch-specific programs not confirmed |
| Pfizer | Immunology company | Infliximab and etrasimod; etrasimod under study for prevention |
| Bausch Health | Antibiotic supplier | Rifaximin (Xifaxan) through Salix, under study for recurrent pouchitis |
| Teva Pharmaceutical | Generic maker | Generic antibiotics; pouchitis-specific supply not confirmed |
| Exegi Pharma | Probiotic and microbiome developer | Visbiome probiotic and EXE-346 live biotherapeutic in pouch trials |
Pouchitis value follows the chronic patient
Credence Research's view is that pouchitis treatment value follows the chronic patient, not the acute flare, and that this will hold through 2035. The largest new revenue lies in maintenance biologics for antibiotic-refractory disease and, later, in IL-23 inhibitors and oral small molecules. A U.S. pouchitis label is the single largest swing factor, because it would turn off-label prescribing into routine reimbursement, while the main risk is biosimilar price erosion. Investors should watch pouch-specific trial readouts, the pediatric vedolizumab study and any U.S. filing for a pouchitis indication.
How Credence Research sized pouchitis drug spending
The report uses 2025 as the base year and forecasts to 2035, with CAGR calculated over 2025–2035. Market values come from Credence Research's market model, built from pouch patient numbers in the published clinical literature, rates of acute and chronic pouchitis and treatment patterns by therapy line; segment and regional splits are Credence Research estimates. Supporting evidence comes from PubMed-indexed studies, regulator labels, trial registries and company announcements, although off-label prescribing limits precision in some countries.
Maintenance therapy and a possible U.S. label set the pace
Through 2035, spending will shift further toward maintenance therapy for chronic pouchitis, while antibiotics keep their role in acute flares at low prices. IL-23 inhibitors and oral small molecules will join vedolizumab as pouch data mature, and microbiome products could reach the market from a small base. Asia Pacific will gain share as ulcerative colitis rates rise, while North America remains the largest region. The pace will depend on whether a U.S. pouchitis label arrives, how quickly biosimilars reach vedolizumab and whether prevention trials succeed.
Frequently Asked Questions
What was the size of the pouchitis treatment market in 2025?
What is the forecast value and CAGR of the pouchitis treatment market?
What is driving demand for pouchitis treatment?
Which region holds the largest share of the pouchitis treatment market?
Which drug class leads the pouchitis treatment market?
Is any drug approved for chronic pouchitis?
Who are the major companies in the pouchitis treatment market?
What challenges could slow the pouchitis treatment market?
Table of Content
Chapter 1 Market Segmentation
- 1.1 Segmentation Framework
- 1.1.1 Product and Service Classification
- 1.1.2 Application and End-Use Classification
- 1.1.3 Technology and Solution Classification
- 1.1.4 Customer and Distribution Channel Classification
- 1.1.5 Geographic Segmentation
- 1.1.6 Market Segment Definitions and Boundaries
- 1.2 By Drug Class
- 1.2.1 Biologics & Targeted Small Molecules
- 1.2.2 Antibiotics
- 1.2.3 Probiotics
- 1.2.4 Corticosteroids & 5-ASA
- 1.2.5 Microbiome & Other Therapies
- 1.3 By Disease Type
- 1.3.1 Chronic Antibiotic-Refractory Pouchitis
- 1.3.2 Chronic Antibiotic-Dependent Pouchitis
- 1.3.3 Acute Pouchitis
Chapter 2 Introduction
- 2.1 Report Objectives and Scope
- 2.2 Product Definition and Industry Terminology
- 2.3 Market Inclusions and Exclusions
- 2.4 Research Process
- 2.4.1 Primary Research and Expert Interviews
- 2.4.2 Secondary Research and Source Review
- 2.4.3 Top-Down and Bottom-Up Estimation
- 2.4.4 Data Triangulation and Verification
- 2.5 Market Size Measurement Basis
- 2.5.1 2025: USD 386.4 million → 2035: USD 641.5 million
- 2.6 Historical and Forecast Reference Periods
- 2.6.1 Historical Period: 2018-2025
- 2.6.2 Base Year: 2025
- 2.6.3 Forecast Period: 2025-2035
- 2.7 Research Assumptions and Limitations
Chapter 3 Executive Summary
- 3.1 Market Snapshot and Key Findings
- 3.2 Base-Year Market Size, 2025
- 3.3 Forecast Market Size, 2035
- 3.4 Revenue and Volume Growth Outlook
- 3.5 Key Demand and Supply Indicators
- 3.6 Leading Market Segments
- 3.7 Fastest-Growing Market Opportunities
- 3.8 Regional Performance Highlights
- 3.9 Technology and Industry Transformation
- 3.10 Competitive Landscape Summary
- 3.11 Analyst View and Strategic Implications
Chapter 4 Global Pouchitis Treatment Market Trends and Developments
- 4.1 Historical Industry Development, 2018-2025
- 4.2 Recent Market Trends and Developments
- 4.3 Demand and Customer Behavior Trends
- 4.4 Technology and Product Innovation
- 4.5 Artificial Intelligence, Automation and Digitalization
- 4.6 Local Manufacturing and Supply Chain Realignment
- 4.7 Industry Partnerships, Mergers and Acquisitions
- 4.8 Sustainability and Circular Economy Developments
- 4.9 Government and Private Sector Investment Trends
- 4.10 Emerging Business Models and Commercialization
- 4.11 Industry Developments and Announcements
Chapter 5 Global Pouchitis Treatment Market Production, Supply and Demand Analysis
- 5.1 Demand Trend and Consumption Analysis, 2018-2025
- 5.2 Demand Forecast, 2025-2035
- 5.3 Production and Output Trend, 2018-2025
- 5.4 Production and Output Forecast, 2025-2035
- 5.5 Installed Capacity and Capacity Utilization
- 5.6 Company-Wise Production Plants and Statistics
- 5.6.1 Installed Production Capacity
- 5.6.2 Actual Production
- 5.6.3 Planned Capacity and Expansion Targets
- 5.7 Supply Chain Structure and Procurement Trends
- 5.8 Supply-Demand Gap and Bottlenecks
- 5.9 Import Dependence and Sourcing Structure
- 5.10 Contract Manufacturing and Outsourcing
- 5.11 Regional Supply and Demand Concentration
Chapter 6 Global Pouchitis Treatment Market Pricing Analysis
- 6.1 Pricing Structure and Measurement
- 6.2 Historical Pricing Trends, 2018-2025
- 6.3 Pricing Outlook, 2025-2035
- 6.4 Average Selling Price and Unit Economics
- 6.5 Pricing by Product and Market Segment
- 6.6 Geographic Pricing Differences
- 6.7 Key Input, Energy, Labor and Logistics Costs
- 6.8 Contract Pricing and Purchasing Models
- 6.9 Pricing Sensitivity and Competitive Positioning
- 6.10 Price, Margin and Profitability Implications
Chapter 7 Global Pouchitis Treatment Market Dynamics
- 7.1 Market Growth Drivers
- 7.1.1 Demand-Side Drivers
- 7.1.2 Technology and Innovation Drivers
- 7.1.3 Infrastructure and Investment Drivers
- 7.1.4 Regulatory and Policy Drivers
- 7.2 Market Restraints
- 7.2.1 Cost and Affordability Constraints
- 7.2.2 Technology and Adoption Barriers
- 7.2.3 Supply Chain and Operational Constraints
- 7.3 Market Challenges
- 7.3.1 Competitive Pressure and Margin Erosion
- 7.3.2 Skills, Infrastructure and Implementation Gaps
- 7.4 Emerging Market Opportunities
- 7.5 Market Dynamics Impact and Time-Horizon Assessment
Chapter 8 Global Pouchitis Treatment Value Chain Analysis
- 8.1 Industry Value Chain Overview
- 8.2 Upstream Suppliers and Critical Inputs
- 8.3 Technology and Component Providers
- 8.4 Manufacturing or Service Delivery
- 8.5 Distribution, Channel Partners and Integrators
- 8.6 Downstream Applications and End Users
- 8.7 Value Addition and Profit Pools
- 8.8 Vertical Integration and Outsourcing
- 8.9 Supplier Concentration and Risk
- 8.10 Supply Chain Localization and Resilience
Chapter 9 Global Pouchitis Treatment Market Regulations and Policies
- 9.1 Relevant Laws, Standards and Compliance Frameworks
- 9.2 Product, Service, Safety and Quality Requirements
- 9.3 Government Policies, Incentives and Subsidies
- 9.4 Imports, Exports and Trade Barriers
- 9.5 Public Procurement and Local Content Requirements
- 9.6 Environmental and Sustainability Compliance
- 9.7 Upcoming Policy Changes and Market Implications
Chapter 10 Global Pouchitis Treatment Market Hotspots and Opportunities
- 10.1 Market Opportunity Mapping and Growth Hotspots
- 10.2 High-Growth Applications and Customer Groups
- 10.3 Underserved Markets and White-Space Opportunities
- 10.4 Emerging Technology and Product Opportunities
- 10.5 New Capacity and Investment Hotspots
- 10.6 Market Entry and Expansion Opportunities
- 10.7 Distribution and Partnership Opportunities
- 10.8 Near-Term and Long-Term Commercial Potential
- 10.9 Opportunity Attractiveness and Execution Risks
Chapter 11 Global Pouchitis Treatment Market Outlook, 2025-2035
- 11.1 Market Size and Analysis
- 11.1.1 Revenue (Market Measurement: 2025: USD 386.4 million → 2035: USD 641.5 million)
- 11.1.2 Market Volume and Quantity Sold
- 11.1.3 Historical Market Size, 2018-2025
- 11.1.4 Base-Year Market Size, 2025
- 11.2 Market Forecast, 2025-2035
- 11.2.1 Revenue Forecast to 2035
- 11.2.2 Volume Forecast to 2035
- 11.2.3 CAGR and Year-on-Year Growth
- 11.2.4 Incremental Revenue Opportunity
- 11.3 Forecast Assumptions and Scenario Analysis
- 11.3.1 Base-Case Forecast
- 11.3.2 Optimistic and Conservative Scenarios
- 11.3.3 Technology, Pricing and Policy Sensitivities
- 11.4 Market Attractiveness and Growth Outlook
Chapter 12 Global Pouchitis Treatment Market Segmentation and Outlook
- 12.1 Segmentation Summary and Market Shares, 2025
- 12.2 Largest and Fastest-Growing Segments
- 12.3 By Drug Class - Market Size and Forecast, 2025-2035
- 12.3.1 Segment Definition and Scope
- 12.3.2 Historical Market Size, 2018-2025
- 12.3.3 Revenue Forecast, 2025-2035
- 12.3.4 Volume Forecast, 2025-2035
- 12.3.5 Base-Year Market Share, 2025
- 12.3.6 Segment CAGR and Growth Drivers
- 12.3.7 Subsegment Market Size and Forecast
- 12.3.7.1 Biologics & Targeted Small Molecules
- 12.3.7.2 Antibiotics
- 12.3.7.3 Probiotics
- 12.3.7.4 Corticosteroids & 5-ASA
- 12.3.7.5 Microbiome & Other Therapies
- 12.3.8 Subsegment Pricing and Adoption Trends
- 12.3.9 Leading Suppliers and Competition
- 12.3.10 Regional Demand and Opportunities
- 12.4 By Disease Type - Market Size and Forecast, 2025-2035
- 12.4.1 Segment Definition and Scope
- 12.4.2 Historical Market Size, 2018-2025
- 12.4.3 Revenue Forecast, 2025-2035
- 12.4.4 Volume Forecast, 2025-2035
- 12.4.5 Base-Year Market Share, 2025
- 12.4.6 Segment CAGR and Growth Drivers
- 12.4.7 Subsegment Market Size and Forecast
- 12.4.7.1 Chronic Antibiotic-Refractory Pouchitis
- 12.4.7.2 Chronic Antibiotic-Dependent Pouchitis
- 12.4.7.3 Acute Pouchitis
- 12.4.8 Subsegment Pricing and Adoption Trends
- 12.4.9 Leading Suppliers and Competition
- 12.4.10 Regional Demand and Opportunities
- 12.5 Segment Growth Comparison
- 12.6 Segment Attractiveness and Priority Matrix
Chapter 13 Global Pouchitis Treatment Geographic Market Outlook, 2025-2035
- 13.1 Regional Market Size and Share, 2025
- 13.2 Regional Market Forecast, 2025-2035
- 13.3 Regional Pricing, Production and Demand Differences
- 13.4 North America
- 13.4.1 United States
- 13.4.2 Canada
- 13.4.3 Mexico
- 13.5 Europe
- 13.5.1 Germany
- 13.5.2 France
- 13.5.3 Italy
- 13.5.4 United Kingdom
- 13.5.5 Spain
- 13.5.6 Poland
- 13.5.7 Russia
- 13.5.8 Netherlands
- 13.5.9 Belgium
- 13.5.10 Sweden
- 13.5.11 Denmark
- 13.5.12 Norway
- 13.5.13 Rest of Europe
- 13.6 Asia Pacific
- 13.6.1 China
- 13.6.2 India
- 13.6.3 Japan
- 13.6.4 South Korea
- 13.6.5 Thailand
- 13.6.6 Indonesia
- 13.6.7 Vietnam
- 13.6.8 Malaysia
- 13.6.9 Australia
- 13.6.10 Rest of Asia Pacific
- 13.7 Latin America
- 13.7.1 Brazil
- 13.7.2 Argentina
- 13.7.3 Colombia
- 13.7.4 Chile
- 13.7.5 Rest of Latin America
- 13.8 Middle East
- 13.8.1 Saudi Arabia
- 13.8.2 United Arab Emirates
- 13.8.3 Turkey
- 13.8.4 Israel
- 13.8.5 Iran
- 13.8.6 Rest of the Middle East
- 13.9 Africa
- 13.9.1 South Africa
- 13.9.2 Egypt
- 13.9.3 Nigeria
- 13.9.4 Morocco
- 13.9.5 Rest of Africa
- 13.10 Regional Investment, Policy and Supply Chain Differences
- 13.11 Regional Competitive Landscape
- 13.12 Geographic Growth Hotspots
Chapter 14 Global Pouchitis Treatment Technology, Innovation and Sustainability Outlook
- 14.1 Technology Landscape and Maturity
- 14.2 Product, Process and Service Innovation
- 14.3 AI, Automation and Digital Tools in the Industry
- 14.4 Technology Adoption and Performance Benchmarking
- 14.5 Innovation Pipeline and R&D Investment
- 14.6 Patent and Intellectual Property Trends
- 14.7 Energy Efficiency and Resource Management
- 14.8 Sustainability, Recycling and Circularity
- 14.9 Technology Roadmap, 2025-2035
- 14.10 Risks of Obsolescence and Technology Substitution
Chapter 15 Global Pouchitis Treatment Market Key Strategic Imperatives
- 15.1 Growth and Market Entry Priorities
- 15.2 High-Return Products and Segments
- 15.3 Pricing, Profitability and Cost Optimization
- 15.4 Technology Investment and Product Differentiation
- 15.5 Supply Chain Localization and Resilience
- 15.6 Distribution and Customer Acquisition
- 15.7 Partnership, Acquisition and Capacity Strategy
- 15.8 Regional Expansion Priorities
- 15.9 Short-, Medium- and Long-Term Actions
Chapter 16 Competition Outlook
- 16.1 Industry Competition Characteristics
- 16.2 Market Structure and Concentration
- 16.3 Market Share and Competitive Positioning, 2025
- 16.4 Company-Wise Revenue and Product Benchmarking
- 16.5 Production and Service Capacity Benchmarking
- 16.6 Technology, Pricing and Differentiation
- 16.7 Regional Footprint and Distribution Strength
- 16.8 Mergers, Acquisitions and Strategic Alliances
- 16.9 New Entrants and Competitive Threats
- 16.10 Porter's Five Forces and Industry Attractiveness
- 16.11 Competitive Outlook, 2025-2035
Chapter 17 Company Profiles
- 17.1 Company Coverage and Selection Criteria
- 17.2 Takeda Pharmaceutical
- 17.2.1 Business Description
- 17.2.2 Company Ownership and Geographic Presence
- 17.2.3 Product and Service Portfolio
- 17.2.4 Manufacturing and Operating Footprint
- 17.2.5 Production Capacity and Expansion Plans
- 17.2.6 Financial Performance and Investment
- 17.2.7 Market Share and Competitive Position
- 17.2.8 Technology and Innovation Capabilities
- 17.2.9 Strategic Alliances or Partnerships
- 17.2.10 Recent Developments
- 17.2.11 Growth Strategy and Outlook
- 17.3 Johnson & Johnson
- 17.4 Eli Lilly
- 17.5 AbbVie
- 17.6 Pfizer
- 17.7 Bausch Health
- 17.8 Teva Pharmaceutical
- 17.9 Exegi Pharma
- 17.10 Other Relevant Market Participants
Note: Every listed company is profiled on the structure shown under the first company. The company list is preliminary and may change based on research findings, market developments, data availability and client requirements.
Chapter 18 Disclaimer
- 18.1 Research and Forecast Disclaimer
- 18.2 Data Source and Estimation Limitations
Note: The depth of individual sections depends on data availability for this market. Volume, capacity, trade and other unit-based metrics are included where applicable.

