
Diabetic Nephropathy Market Overview:
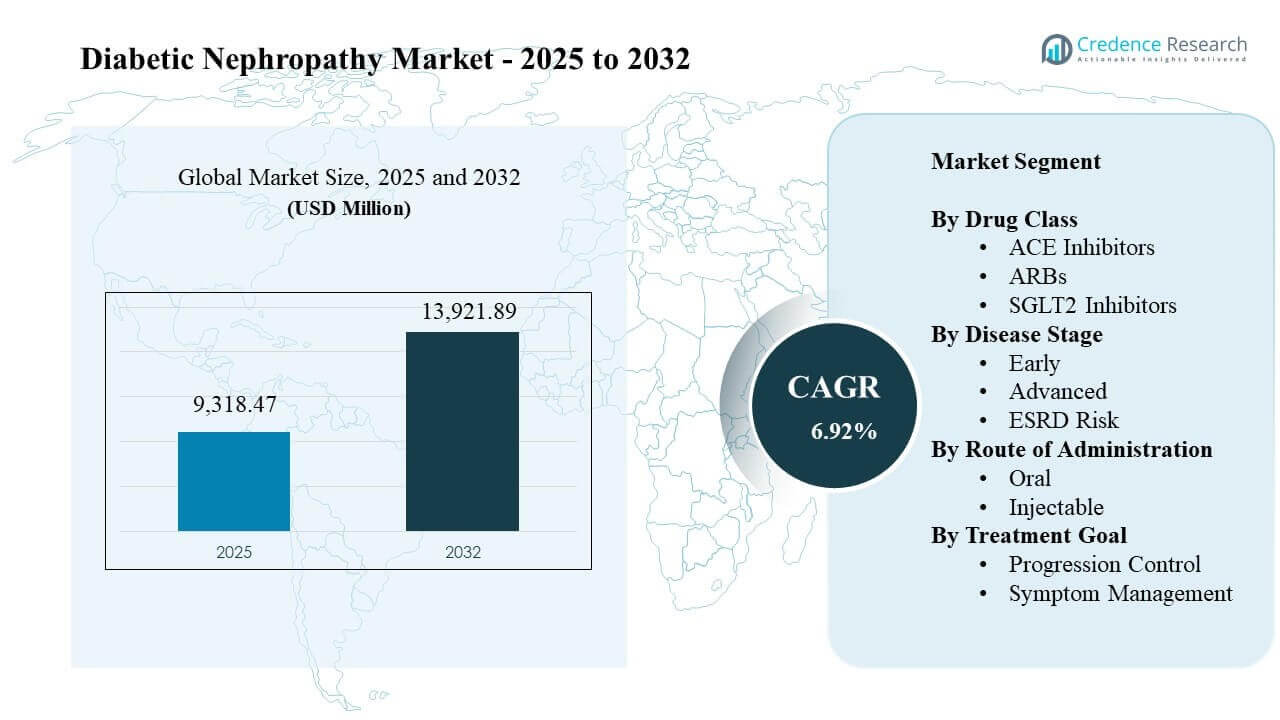
The global Diabetic Nephropathy Market size was estimated at USD 9,318.47 million in 2025 and is expected to reach USD 13,921.89 million by 2032, growing at a CAGR of 6.92% from 2025 to 2032. The strongest growth driver is the rapid shift toward kidney-protective, outcomes-focused diabetes care, where clinicians prioritize therapies that slow renal decline and reduce cardio-renal risk in large type 2 diabetes populations. Expanding screening for albuminuria and eGFR decline in routine diabetes management is also increasing treated prevalence, especially as payers and guidelines reinforce earlier intervention to delay progression and reduce dialysis-transition risk.
| REPORT ATTRIBUTE | DETAILS |
|---|---|
| Historical Period | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2032 |
| Diabetic Nephropathy Market Size 2025 | USD 9,318.47 million |
| Diabetic Nephropathy Market, CAGR | 6.92% |
| Diabetic Nephropathy Market Size 2032 | USD 13,921.89 million |
Key Market Trends & Insights
- The market is projected to expand from USD 9,318.47 million (2025) to USD 13,921.89 million (2032) at a 6.92% CAGR (2025–2032).
- North America accounted for the largest regional share at 41.9% in 2025, supported by strong adoption of guideline-aligned renal protection strategies.
- Asia Pacific reached 27.4% share in 2025, reflecting rising diabetes prevalence, improving CKD screening, and expanding access to modern therapies.
- Europe represented 22.1% share in 2025, underpinned by structured chronic-disease pathways and broad use of renin-angiotensin system management.
- ACE inhibitors led the drug-class mix with 31.6% share in 2025, reflecting durable first-line use for blood pressure and proteinuria control.
Segment Analysis
Therapy selection in the Diabetic Nephropathy Market is increasingly organized around measurable renal outcomes, with progression control becoming the dominant clinical objective across early and advanced stages. Earlier identification of albuminuria and declining eGFR is expanding treatable cohorts, which supports sustained demand for foundational renin-angiotensin system therapies and accelerates uptake of newer kidney-protective agents. Prescribing decisions often balance long-term renal benefit, comorbidity burden, and payer access, which shapes class switching and combination use over time.
Demand is also influenced by where care occurs, with primary care managing large volumes of early-stage patients and specialists guiding intensification for advanced-stage and ESRD-risk cohorts. Oral therapies remain central to chronic management because they scale well across large populations and support adherence in long-duration regimens. Injectable therapies can expand their role as kidney-outcome labeling and specialist-driven use broadens, particularly for patients with high cardio-renal risk and multi-morbidity.
By Drug Class Insights
ACE Inhibitors accounted for the largest share of 31.6% in 2025. ACE inhibitors remain widely used because clinicians value established renoprotective evidence and broad familiarity for managing hypertension and proteinuria in diabetes. Long-standing prescribing patterns and generic availability support access across both mature and cost-sensitive health systems. Class leadership also benefits from consistent placement in care pathways that start with foundational blood pressure control before adding newer agents.
By Disease Stage Insights
Early-stage management tends to hold the broadest treated base because screening expansion and routine diabetes follow-up identify albuminuria sooner and trigger earlier therapy initiation. Advanced-stage cohorts drive higher therapy intensity because patients face greater progression risk and higher comorbidity load that requires layered management. ESRD-risk pathways increase demand for regimens focused on slowing decline and reducing hospitalization, with closer monitoring and tighter coordination across endocrinology and nephrology settings.
By Route of Administration Insights
Oral accounted for the largest share of 56.2% in 2025. Oral therapies lead because they support long-term adherence and are easier to initiate and maintain across large type 2 diabetes populations in primary care. Dispensing and reimbursement processes are typically simpler for oral chronic therapies, which improves continuity of treatment. Oral dominance is further reinforced by the role of daily regimens in progression-control strategies, particularly when therapy layering is required over time.
By Treatment Goal Insights
Progression control is the central organizing goal for most care pathways because delaying renal decline reduces total cost of care and lowers the probability of dialysis transition. Clinical protocols increasingly emphasize earlier intervention to preserve kidney function and reduce cardio-renal events, which promotes proactive therapy initiation and escalation. Symptom management remains important in later-stage patients, where edema, blood pressure variability, and multi-morbidity shape supportive care choices and monitoring intensity.
Diabetic Nephropathy Market Drivers
Expanding diabetes prevalence and longer disease duration
Rising type 2 diabetes prevalence and longer survival are increasing the pool of patients exposed to chronic hyperglycemia and hypertension, which elevates the risk of kidney damage over time. Larger treated populations translate into higher screening volumes and more frequent detection of albuminuria and eGFR decline. As clinicians diagnose kidney involvement earlier, therapy is initiated sooner and maintained for longer durations. This dynamic lifts prescription volumes and supports sustained demand across foundational and newer kidney-protective regimens.
- For instance, AstraZeneca’s dapagliflozin (Farxiga) demonstrated a 39% relative risk reduction in sustained eGFR decline, end-stage kidney disease, or renal death in the DAPA-CKD trial, highlighting increased long-term utilization as patient pools expand.
Shift toward outcomes-based kidney protection in routine care
Care standards are increasingly centered on preventing progression rather than reacting to late-stage complications. Clinicians are aligning medication choices with renal-risk reduction and cardio-renal protection goals, which supports therapy intensification and combination approaches over time. Payers and integrated delivery systems also favor strategies that reduce hospitalization and delay dialysis transitions. As a result, treatment algorithms are becoming more structured and proactive, strengthening adoption of therapies positioned for progression control.
Earlier screening and pathway-driven identification
Wider use of albumin-to-creatinine ratio testing and routine renal-function monitoring in diabetes management is expanding diagnosed prevalence. Early identification increases the number of patients eligible for therapy before irreversible decline occurs. Better risk stratification also improves targeting of intensification, which can increase persistence and refill continuity. This driver is especially important in health systems that promote chronic-disease registries and standardized follow-up intervals.
- For instance, Roche’s Cobas platform enables automated urine albumin-to-creatinine ratio testing with throughput exceeding 1,000 tests per hour in centralized labs, supporting large-scale early detection and standardized screening workflows.
Broader access and scaling through oral therapy dominance
Oral regimens support scale because they fit chronic, primary-care-led management and reduce logistical barriers linked to administration. Higher oral utilization also supports adherence in long-duration therapy, which improves continuity and long-term treatment exposure. As more therapies are integrated into oral-based renal-risk management pathways, the addressable treated base expands. These factors support market growth across early-stage cohorts where long-term persistence is a key demand lever.
Diabetic Nephropathy Market Challenges
Pricing pressure and formulary restrictions can compress margins and slow uptake of newer therapies, particularly in cost-sensitive markets and public procurement environments. Payers often require step therapy, prior authorization, or strict eligibility criteria, which delays intensification for progression control. Treatment adherence remains challenging because diabetic nephropathy requires long-duration regimens and frequent monitoring. Care fragmentation across endocrinology, primary care, and nephrology can also create gaps in follow-up that reduce persistence.
Clinical heterogeneity complicates standardized treatment because progression risk varies widely by comorbidities, baseline renal function, and patient behavior. Late diagnosis remains a constraint in markets with limited screening coverage, which concentrates demand in advanced-stage cohorts and raises the burden of complications. Polypharmacy can increase discontinuation risk, especially in older patients managing cardiovascular disease, hypertension, and diabetes simultaneously. Monitoring intensity and patient education requirements also add operational complexity for providers and health systems.
- For instance, Bayer’s finerenone (Kerendia) showed an 18% reduction in the composite outcome of kidney failure, sustained ≥40% decrease in eGFR, or renal death in the FIDELIO-DKD study, but its real-world effectiveness depends heavily on consistent potassium monitoring and patient adherence, highlighting implementation challenges in routine clinical settings.
Diabetic Nephropathy Market Trends and Opportunities
Combination strategies are gaining momentum as clinicians layer therapies to improve renal-risk management, support blood pressure control, and address cardio-renal outcomes. This trend creates opportunities for companies to position complementary regimens and generate differentiated evidence for progression control in high-risk cohorts. Earlier intervention is becoming more common as screening improves, which expands the treatable base and lengthens therapy duration. Product strategies that simplify initiation and persistence can improve adoption across primary care.
Growth opportunities are strengthening in Asia Pacific as healthcare access expands and chronic-disease programs improve testing and follow-up. Providers are also increasing attention to risk stratification and patient engagement, which can support adherence and reduce progression-related costs. Digital tools that improve monitoring and care coordination can help sustain persistence, particularly for early-stage patients. Companies that align evidence, access, and provider education with pathway-based care can capture share as treatment algorithms mature.
- For instance, Roche’s digital health platform integrated with its Accu-Chek solutions has supported remote glucose monitoring programs in Asia, contributing to adherence improvements of over 20% in connected care pilots and enabling more consistent longitudinal patient tracking in chronic disease management.
Regional Insights
North America
North America held 41.9% share in 2025, supported by high diagnosis rates, established chronic-disease pathways, and strong adoption of guideline-aligned renal protection strategies. Large treated type 2 diabetes populations and broad access to specialist care support earlier intensification for progression control. Payer focus on reducing hospitalization and delaying ESRD transition encourages therapy layering and monitoring. Competitive differentiation often centers on outcomes evidence, access positioning, and real-world utilization support.
Europe
Europe accounted for 22.1% share in 2025, supported by structured reimbursement frameworks and strong integration of renal monitoring in diabetes care pathways. Clinical practice favors standardized approaches to blood pressure and proteinuria control, which sustains demand for foundational therapies. Uptake of newer regimens depends on country-level reimbursement decisions and pathway updates. Manufacturers compete through evidence generation, health-economic positioning, and alignment with protocol-driven care.
Asia Pacific
Asia Pacific represented 27.4% share in 2025, driven by expanding diabetes prevalence, improving CKD screening coverage, and rising access to modern therapies in major markets. Growth is supported by increasing awareness of early intervention and larger volumes of newly diagnosed patients entering care pathways. Hospital-driven initiation and specialist influence remain important in many countries, particularly for advanced-stage cohorts. Companies that strengthen access strategies and provider education can scale faster as monitoring and follow-up improve.
Latin America
Latin America reached 5.1% share in 2025, reflecting improving diagnosis in major urban centers but uneven access to consistent monitoring and advanced therapies across countries. Demand is concentrated in systems with stronger chronic-care infrastructure and broader reimbursement coverage. Treatment continuity can be limited by affordability constraints and care fragmentation, which affects adherence and progression-control strategies. Opportunities center on expanding screening, improving follow-up pathways, and increasing access to kidney-protective regimens.
Middle East & Africa
The Middle East & Africa held 3.5% share in 2025, with demand shaped by wide variation in healthcare capacity and access across markets. Advanced-stage presentation can be more common where screening and follow-up are inconsistent, increasing the burden of complications. Select higher-income markets can show faster adoption of modern therapies, but scale remains limited across the broader region. Strengthening chronic-disease programs and renal monitoring infrastructure can expand early-stage identification and treated prevalence.
Competitive Landscape
Competition in the Diabetic Nephropathy Market is shaped by outcomes-driven positioning, formulary access strategies, and evidence generation that supports progression control and cardio-renal risk reduction. Market participants compete by aligning therapy portfolios with guideline pathways, strengthening real-world utilization support, and building clinician education that improves persistence. Differentiation is reinforced through combination strategies, risk-stratified patient targeting, and partnerships that improve monitoring and care coordination across primary and specialty settings.
AstraZeneca is positioned with a strategy that emphasizes scaling kidney-protective therapy use through broad clinical adoption pathways and access execution across major markets. AstraZeneca’s approach typically centers on reinforcing prescriber confidence with outcomes evidence, supporting integration into diabetes and CKD care algorithms, and sustaining utilization through long-duration chronic management. This positioning aligns with progression-control goals that are increasingly prioritized by payers and providers. AstraZeneca’s competitive emphasis also benefits from targeting large treated type 2 diabetes cohorts where adherence and persistence drive recurring demand.
The industry research and growth report includes detailed analyses of the competitive landscape of the market and information about key companies, including:
- AstraZeneca
- Boehringer Ingelheim
- Eli Lilly
- Novo Nordisk
- Pfizer
- Bayer
- Novartis
- Sanofi
- AbbVie
- Roche
Qualitative and quantitative analysis of companies has been conducted to help clients understand the wider business environment as well as the strengths and weaknesses of key industry players. Data is qualitatively analyzed to categorize companies as pure play, category-focused, industry-focused, and diversified; it is quantitatively analyzed to categorize companies as dominant, leading, strong, tentative, and weak.
Recent Developments
- In April 2026, DelveInsight reported that more than 20 key companies, including Lexicon Pharmaceuticals, Glenmark Pharmaceuticals, Helixmith, Regenacy Pharmaceuticals, Vertex Pharmaceuticals, Daiichi Sankyo, Eli Lilly and Company, and others, are actively developing over 25 therapies targeting diabetic nephropathy, with ongoing collaborations, licensing deals, funding rounds, and development partnerships shaping the current market and clinical pipeline landscape.
- In September 2025, Walden Biosciences, a biotech company focused on kidney diseases including diabetic nephropathy, initiated a set of strategic collaborations to support its Phase 2 study of WAL0921, engaging former US FDA director Dr. Norman Stockbridge as a regulatory advisor and partnering with the patient‑advocacy group NephCure to enhance awareness and recruitment for the trial, with initial data anticipated in late 2025 or early 2026.
- In March 2024, Hua Medicine announced that it would focus on advancing its type 2 diabetes drug Huatangning (dorzagliatin) for diabetic kidney patients in the United States, following multiple Phase I trials and an investigational new drug submission to the US FDA, building on its existing commercialization collaboration with Bayer for the product’s twice‑daily formulation in China.
Report Scope
| Report Attribute | Details |
| Market size value in 2025 | USD 9,318.47 million |
| Revenue forecast in 2032 | USD 13,921.89 million |
| Growth rate (CAGR) | 6.92% (2025–2032) |
| Base year | 2025 |
| Forecast period | 2026–2032 |
| Quantitative units | USD million |
| Segments covered | By Drug Class Outlook: ACE inhibitors, ARBs, and SGLT2 inhibitors competing via outcomes evidence, cost access, and combination positioning.; By Disease Stage Outlook: early detection and progression prevention shaping therapy intensity across early, advanced, and ESRD-risk cohorts.; By Route of Administration Outlook: oral dominance sustained by adherence and scale, with injectables expanding via kidney-outcome labeling.; By Treatment Goal Outlook: progression-control focus rising with outcomes-based reimbursement and guideline alignment. |
| Regional scope | North America, Europe, Asia Pacific, Latin America, Middle East & Africa |
| Key companies profiled | AstraZeneca, Boehringer Ingelheim, Eli Lilly, Novo Nordisk, Pfizer, Bayer, Novartis, Sanofi, AbbVie, Roche |
| No.of Pages | 334 |
Segmentation
By Drug Class
- ACE Inhibitors
- ARBs
- SGLT2 Inhibitors
By Disease Stage
- Early
- Advanced
- ESRD Risk
By Route of Administration
- Oral
- Injectable
By Treatment Goal
- Progression Control
- Symptom Management
By Region
- North America
- U.S.
- Canada
- Mexico
- Europe
- Germany
- France
- U.K.
- Italy
- Spain
- Rest of Europe
- Asia Pacific
- China
- Japan
- India
- South Korea
- South-east Asia
- Rest of Asia Pacific
- Latin America
- Brazil
- Argentina
- Rest of Latin America
- Middle East & Africa
- GCC Countries
- South Africa
- Rest of the Middle East and Africa

Request a Free Sample
Fill in your details and we'll send you a free sample report.
- Sample data tables & charts
- Research methodology
Market Dynamics
Expanding diabetes prevalence and longer disease duration
Rising type 2 diabetes prevalence and increased patient survival are enlarging the population at risk for diabetic nephropathy, leading to higher screening rates and earlier detection of kidney involvement. This results in more patients being treated for longer periods, boosting overall prescription volumes and market growth.
Shift toward outcomes-based kidney protection in routine care
Clinical practice is increasingly focused on preventing renal progression rather than managing late-stage complications, driving earlier and more intensive therapy initiation. This proactive approach, reinforced by payer incentives and guidelines, increases adoption of both foundational and newer kidney-protective agents.
Earlier screening and pathway-driven identification
Wider implementation of albuminuria and eGFR testing in diabetes management is expanding the diagnosed and treatable population. Early identification allows for timely intervention, improving patient outcomes and supporting sustained demand for therapies that delay disease progression.
Broader access and scaling through oral therapy dominance
Oral therapies are favored for their ease of use, scalability in primary care, and support for long-term adherence, making them central to chronic management strategies. As more kidney-protective agents become available in oral formulations, the addressable market expands, particularly among early-stage patients.
Combination and layered therapy strategies
Clinicians are increasingly adopting combination regimens to optimize renal and cardio-renal outcomes, especially in high-risk cohorts. This trend supports market growth by increasing therapy intensity and duration, and creates opportunities for companies to differentiate through evidence-based combination approaches.
Need a Custom Version of This Report?
Tailor the scope, geography, or segments to your exact requirements.
- Custom geography or segment scope
- Direct access to our analyst team
Frequently Asked Questions
What is the market size of the Diabetic Nephropathy Market in 2025 and the forecast for 2032?
What is the CAGR for the Diabetic Nephropathy Market during 2025–2032?
What is the largest segment in the Diabetic Nephropathy Market?
What factors are driving growth in the Diabetic Nephropathy Market?
Which companies are profiled in the Diabetic Nephropathy Market report?
Which region leads the Diabetic Nephropathy Market?
Table of Content
Chapter 1 Market Segmentation
- 1.1 Segmentation Framework
- 1.1.1 Product and Service Classification
- 1.1.2 Application and End-Use Classification
- 1.1.3 Technology and Solution Classification
- 1.1.4 Customer and Distribution Channel Classification
- 1.1.5 Geographic Segmentation
- 1.1.6 Market Segment Definitions and Boundaries
- 1.2 By Drug Class
- 1.2.1 ACE Inhibitors
- 1.2.2 ARBs
- 1.2.3 SGLT2 Inhibitors
- 1.3 By Disease Stage
- 1.3.1 Early
- 1.3.2 Advanced
- 1.3.3 ESRD Risk
- 1.4 By Treatment Goal
- 1.4.1 Progression Control
- 1.4.2 Symptom Management
- 1.5 By Route of Administration
- 1.5.1 Oral
- 1.5.2 Injectable
Chapter 2 Introduction
- 2.1 Report Objectives and Scope
- 2.2 Product Definition and Industry Terminology
- 2.3 Market Inclusions and Exclusions
- 2.4 Research Process
- 2.4.1 Primary Research and Expert Interviews
- 2.4.2 Secondary Research and Source Review
- 2.4.3 Top-Down and Bottom-Up Estimation
- 2.4.4 Data Triangulation and Verification
- 2.5 Market Size Measurement Basis
- 2.5.1 2025: USD 9,318.47 million → 2032: USD 13,921.89 million
- 2.6 Historical and Forecast Reference Periods
- 2.6.1 Base Year: 2025
- 2.6.2 Forecast Period: 2025-2032
- 2.7 Research Assumptions and Limitations
Chapter 3 Executive Summary
- 3.1 Market Snapshot and Key Findings
- 3.2 Base-Year Market Size, 2025
- 3.3 Forecast Market Size, 2032
- 3.4 Revenue and Volume Growth Outlook
- 3.5 Key Demand and Supply Indicators
- 3.6 Leading Market Segments
- 3.7 Fastest-Growing Market Opportunities
- 3.8 Regional Performance Highlights
- 3.9 Technology and Industry Transformation
- 3.10 Competitive Landscape Summary
- 3.11 Analyst View and Strategic Implications
Chapter 4 Global Diabetic Nephropathy Market Trends and Developments
- 4.1 Historical Industry Development
- 4.2 Recent Market Trends and Developments
- 4.3 Demand and Customer Behavior Trends
- 4.4 Technology and Product Innovation
- 4.5 Artificial Intelligence, Automation and Digitalization
- 4.6 Local Manufacturing and Supply Chain Realignment
- 4.7 Industry Partnerships, Mergers and Acquisitions
- 4.8 Sustainability and Circular Economy Developments
- 4.9 Government and Private Sector Investment Trends
- 4.10 Emerging Business Models and Commercialization
- 4.11 Industry Developments and Announcements
Chapter 5 Global Diabetic Nephropathy Market Production, Supply and Demand Analysis
- 5.1 Demand Trend and Consumption Analysis
- 5.2 Demand Forecast, 2025-2032
- 5.3 Production and Output Trend
- 5.4 Production and Output Forecast, 2025-2032
- 5.5 Installed Capacity and Capacity Utilization
- 5.6 Company-Wise Production Plants and Statistics
- 5.6.1 Installed Production Capacity
- 5.6.2 Actual Production
- 5.6.3 Planned Capacity and Expansion Targets
- 5.7 Supply Chain Structure and Procurement Trends
- 5.8 Supply-Demand Gap and Bottlenecks
- 5.9 Import Dependence and Sourcing Structure
- 5.10 Contract Manufacturing and Outsourcing
- 5.11 Regional Supply and Demand Concentration
Chapter 6 Global Diabetic Nephropathy Market Pricing Analysis
- 6.1 Pricing Structure and Measurement
- 6.2 Historical Pricing Trends
- 6.3 Pricing Outlook, 2025-2032
- 6.4 Average Selling Price and Unit Economics
- 6.5 Pricing by Product and Market Segment
- 6.6 Geographic Pricing Differences
- 6.7 Key Input, Energy, Labor and Logistics Costs
- 6.8 Contract Pricing and Purchasing Models
- 6.9 Pricing Sensitivity and Competitive Positioning
- 6.10 Price, Margin and Profitability Implications
Chapter 7 Global Diabetic Nephropathy Market Dynamics
- 7.1 Market Growth Drivers
- 7.1.1 Demand-Side Drivers
- 7.1.2 Technology and Innovation Drivers
- 7.1.3 Infrastructure and Investment Drivers
- 7.1.4 Regulatory and Policy Drivers
- 7.2 Market Restraints
- 7.2.1 Cost and Affordability Constraints
- 7.2.2 Technology and Adoption Barriers
- 7.2.3 Supply Chain and Operational Constraints
- 7.3 Market Challenges
- 7.3.1 Competitive Pressure and Margin Erosion
- 7.3.2 Skills, Infrastructure and Implementation Gaps
- 7.4 Emerging Market Opportunities
- 7.5 Market Dynamics Impact and Time-Horizon Assessment
Chapter 8 Global Diabetic Nephropathy Value Chain Analysis
- 8.1 Industry Value Chain Overview
- 8.2 Upstream Suppliers and Critical Inputs
- 8.3 Technology and Component Providers
- 8.4 Manufacturing or Service Delivery
- 8.5 Distribution, Channel Partners and Integrators
- 8.6 Downstream Applications and End Users
- 8.7 Value Addition and Profit Pools
- 8.8 Vertical Integration and Outsourcing
- 8.9 Supplier Concentration and Risk
- 8.10 Supply Chain Localization and Resilience
Chapter 9 Global Diabetic Nephropathy Market Regulations and Policies
- 9.1 Relevant Laws, Standards and Compliance Frameworks
- 9.2 Product, Service, Safety and Quality Requirements
- 9.3 Government Policies, Incentives and Subsidies
- 9.4 Imports, Exports and Trade Barriers
- 9.5 Public Procurement and Local Content Requirements
- 9.6 Environmental and Sustainability Compliance
- 9.7 Upcoming Policy Changes and Market Implications
Chapter 10 Global Diabetic Nephropathy Market Hotspots and Opportunities
- 10.1 Market Opportunity Mapping and Growth Hotspots
- 10.2 High-Growth Applications and Customer Groups
- 10.3 Underserved Markets and White-Space Opportunities
- 10.4 Emerging Technology and Product Opportunities
- 10.5 New Capacity and Investment Hotspots
- 10.6 Market Entry and Expansion Opportunities
- 10.7 Distribution and Partnership Opportunities
- 10.8 Near-Term and Long-Term Commercial Potential
- 10.9 Opportunity Attractiveness and Execution Risks
Chapter 11 Global Diabetic Nephropathy Market Outlook, 2025-2032
- 11.1 Market Size and Analysis
- 11.1.1 Revenue (Market Measurement: 2025: USD 9,318.47 million → 2032: USD 13,921.89 million)
- 11.1.2 Market Volume and Quantity Sold
- 11.1.3 Historical Market Size
- 11.1.4 Base-Year Market Size, 2025
- 11.2 Market Forecast, 2025-2032
- 11.2.1 Revenue Forecast to 2032
- 11.2.2 Volume Forecast to 2032
- 11.2.3 CAGR and Year-on-Year Growth
- 11.2.4 Incremental Revenue Opportunity
- 11.3 Forecast Assumptions and Scenario Analysis
- 11.3.1 Base-Case Forecast
- 11.3.2 Optimistic and Conservative Scenarios
- 11.3.3 Technology, Pricing and Policy Sensitivities
- 11.4 Market Attractiveness and Growth Outlook
Chapter 12 Global Diabetic Nephropathy Market Segmentation and Outlook
- 12.1 Segmentation Summary and Market Shares, 2025
- 12.2 Largest and Fastest-Growing Segments
- 12.3 By Drug Class - Market Size and Forecast, 2025-2032
- 12.3.1 Segment Definition and Scope
- 12.3.2 Historical Market Size
- 12.3.3 Revenue Forecast, 2025-2032
- 12.3.4 Volume Forecast, 2025-2032
- 12.3.5 Base-Year Market Share, 2025
- 12.3.6 Segment CAGR and Growth Drivers
- 12.3.7 Subsegment Market Size and Forecast
- 12.3.7.1 ACE Inhibitors
- 12.3.7.2 ARBs
- 12.3.7.3 SGLT2 Inhibitors
- 12.3.8 Subsegment Pricing and Adoption Trends
- 12.3.9 Leading Suppliers and Competition
- 12.3.10 Regional Demand and Opportunities
- 12.4 By Disease Stage - Market Size and Forecast, 2025-2032
- 12.4.1 Segment Definition and Scope
- 12.4.2 Historical Market Size
- 12.4.3 Revenue Forecast, 2025-2032
- 12.4.4 Volume Forecast, 2025-2032
- 12.4.5 Base-Year Market Share, 2025
- 12.4.6 Segment CAGR and Growth Drivers
- 12.4.7 Subsegment Market Size and Forecast
- 12.4.7.1 Early
- 12.4.7.2 Advanced
- 12.4.7.3 ESRD Risk
- 12.4.8 Subsegment Pricing and Adoption Trends
- 12.4.9 Leading Suppliers and Competition
- 12.4.10 Regional Demand and Opportunities
- 12.5 By Treatment Goal - Market Size and Forecast, 2025-2032
- 12.5.1 Segment Definition and Scope
- 12.5.2 Historical Market Size
- 12.5.3 Revenue Forecast, 2025-2032
- 12.5.4 Volume Forecast, 2025-2032
- 12.5.5 Base-Year Market Share, 2025
- 12.5.6 Segment CAGR and Growth Drivers
- 12.5.7 Subsegment Market Size and Forecast
- 12.5.7.1 Progression Control
- 12.5.7.2 Symptom Management
- 12.5.8 Subsegment Pricing and Adoption Trends
- 12.5.9 Leading Suppliers and Competition
- 12.5.10 Regional Demand and Opportunities
- 12.6 By Route of Administration - Market Size and Forecast, 2025-2032
- 12.6.1 Segment Definition and Scope
- 12.6.2 Historical Market Size
- 12.6.3 Revenue Forecast, 2025-2032
- 12.6.4 Volume Forecast, 2025-2032
- 12.6.5 Base-Year Market Share, 2025
- 12.6.6 Segment CAGR and Growth Drivers
- 12.6.7 Subsegment Market Size and Forecast
- 12.6.7.1 Oral
- 12.6.7.2 Injectable
- 12.6.8 Subsegment Pricing and Adoption Trends
- 12.6.9 Leading Suppliers and Competition
- 12.6.10 Regional Demand and Opportunities
- 12.7 Segment Growth Comparison
- 12.8 Segment Attractiveness and Priority Matrix
Chapter 13 Global Diabetic Nephropathy Geographic Market Outlook, 2025-2032
- 13.1 Regional Market Size and Share, 2025
- 13.2 Regional Market Forecast, 2025-2032
- 13.3 Regional Pricing, Production and Demand Differences
- 13.4 North America
- 13.4.1 United States
- 13.4.2 Canada
- 13.4.3 Mexico
- 13.5 Europe
- 13.5.1 Germany
- 13.5.2 France
- 13.5.3 Italy
- 13.5.4 United Kingdom
- 13.5.5 Spain
- 13.5.6 Poland
- 13.5.7 Russia
- 13.5.8 Netherlands
- 13.5.9 Belgium
- 13.5.10 Sweden
- 13.5.11 Denmark
- 13.5.12 Norway
- 13.5.13 Rest of Europe
- 13.6 Asia Pacific
- 13.6.1 China
- 13.6.2 India
- 13.6.3 Japan
- 13.6.4 South Korea
- 13.6.5 Thailand
- 13.6.6 Indonesia
- 13.6.7 Vietnam
- 13.6.8 Malaysia
- 13.6.9 Australia
- 13.6.10 Rest of Asia Pacific
- 13.7 Latin America
- 13.7.1 Brazil
- 13.7.2 Argentina
- 13.7.3 Colombia
- 13.7.4 Chile
- 13.7.5 Rest of Latin America
- 13.8 Middle East
- 13.8.1 Saudi Arabia
- 13.8.2 United Arab Emirates
- 13.8.3 Turkey
- 13.8.4 Israel
- 13.8.5 Iran
- 13.8.6 Rest of the Middle East
- 13.9 Africa
- 13.9.1 South Africa
- 13.9.2 Egypt
- 13.9.3 Nigeria
- 13.9.4 Morocco
- 13.9.5 Rest of Africa
- 13.10 Regional Investment, Policy and Supply Chain Differences
- 13.11 Regional Competitive Landscape
- 13.12 Geographic Growth Hotspots
Chapter 14 Global Diabetic Nephropathy Technology, Innovation and Sustainability Outlook
- 14.1 Technology Landscape and Maturity
- 14.2 Product, Process and Service Innovation
- 14.3 AI, Automation and Digital Tools in the Industry
- 14.4 Technology Adoption and Performance Benchmarking
- 14.5 Innovation Pipeline and R&D Investment
- 14.6 Patent and Intellectual Property Trends
- 14.7 Energy Efficiency and Resource Management
- 14.8 Sustainability, Recycling and Circularity
- 14.9 Technology Roadmap, 2025-2032
- 14.10 Risks of Obsolescence and Technology Substitution
Chapter 15 Global Diabetic Nephropathy Market Key Strategic Imperatives
- 15.1 Growth and Market Entry Priorities
- 15.2 High-Return Products and Segments
- 15.3 Pricing, Profitability and Cost Optimization
- 15.4 Technology Investment and Product Differentiation
- 15.5 Supply Chain Localization and Resilience
- 15.6 Distribution and Customer Acquisition
- 15.7 Partnership, Acquisition and Capacity Strategy
- 15.8 Regional Expansion Priorities
- 15.9 Short-, Medium- and Long-Term Actions
Chapter 16 Competition Outlook
- 16.1 Industry Competition Characteristics
- 16.2 Market Structure and Concentration
- 16.3 Market Share and Competitive Positioning, 2025
- 16.4 Company-Wise Revenue and Product Benchmarking
- 16.5 Production and Service Capacity Benchmarking
- 16.6 Technology, Pricing and Differentiation
- 16.7 Regional Footprint and Distribution Strength
- 16.8 Mergers, Acquisitions and Strategic Alliances
- 16.9 New Entrants and Competitive Threats
- 16.10 Porter's Five Forces and Industry Attractiveness
- 16.11 Competitive Outlook, 2025-2032
Chapter 17 Company Profiles
- 17.1 Company Coverage and Selection Criteria
- 17.2 AstraZeneca
- 17.2.1 Business Description
- 17.2.2 Company Ownership and Geographic Presence
- 17.2.3 Product and Service Portfolio
- 17.2.4 Manufacturing and Operating Footprint
- 17.2.5 Production Capacity and Expansion Plans
- 17.2.6 Financial Performance and Investment
- 17.2.7 Market Share and Competitive Position
- 17.2.8 Technology and Innovation Capabilities
- 17.2.9 Strategic Alliances or Partnerships
- 17.2.10 Recent Developments
- 17.2.11 Growth Strategy and Outlook
- 17.3 Boehringer Ingelheim
- 17.4 Eli Lilly
- 17.5 Novo Nordisk
- 17.6 Pfizer
- 17.7 Bayer
- 17.8 Novartis
- 17.9 Sanofi
- 17.10 AbbVie
- 17.11 Roche
- 17.12 Other Relevant Market Participants
Note: Every listed company is profiled on the structure shown under the first company. The company list is preliminary and may change based on research findings, market developments, data availability and client requirements.
Chapter 18 Disclaimer
- 18.1 Research and Forecast Disclaimer
- 18.2 Data Source and Estimation Limitations
Note: The depth of individual sections depends on data availability for this market. Volume, capacity, trade and other unit-based metrics are included where applicable.

